Spine Pain Treatment in Manhattan and NYC

Spine pain can involve the neck, upper back, mid back, low back, sacroiliac joints, nerves, muscles, inflammation, hypermobility, or chronic pain pathways. MPM provides diagnosis-first evaluation to identify what may be driving pain before recommending treatment.

Learn how Dr. Aranguren evaluates spine pain, identifies its underlying causes, and develops personalized treatment plans to help patients reduce pain and improve function.

Understanding Spine Pain

Spine pain is not one diagnosis. It can involve the neck, back, discs, nerves, facet joints, sacroiliac joints, muscles, ligaments, inflammatory conditions, hypermobility, or chronic pain sensitization. Some patients have pain that stays in the spine, while others have pain that travels into the arm, ribs, hip, pelvis, buttock, or leg.

At Manhattan Pain Medicine (MPM), spine pain evaluation begins with identifying the most likely pain generator. The goal is to determine whether symptoms are mechanical, nerve-related, inflammatory, SI joint-related, hypermobility-related, muscular, postural, postsurgical, or part of a more complex chronic pain pattern.

For patients looking for spine pain treatment in Manhattan or NYC, MPM focuses on careful diagnosis, imaging review, coordinated care, and individualized treatment planning rather than generic back pain relief.

Specialist Care for Complex Spine Pain

MPM evaluates spine pain by reviewing the patient’s history, pain location, symptom pattern, prior imaging, prior injections, physical therapy response, neurologic symptoms, inflammatory features, joint mobility, and functional limitations.

Spine pain may overlap with sciatica, herniated discs, spinal stenosis, spondylosis, spondylolisthesis, facet-mediated back pain, sacroiliac joint dysfunction, inflammatory arthritis, seronegative spondyloarthropathy, hypermobility, EDS, slipping rib syndrome, thoracic outlet syndrome, and tethered cord concerns. When needed, MPM coordinates care with spine specialists, rheumatology, orthopedics, neurology, rehabilitation, physical therapy, and other clinicians.

Why Spine Pain Can Persist

Spine pain can continue even after rest, medication, physical therapy, chiropractic care, imaging, or injections because the true pain generator may not have been fully identified. A disc finding on MRI may not explain all symptoms. Mild imaging changes may still be painful in the right clinical context. Severe pain can also come from the SI joint, facet joints, nerve irritation, muscle guarding, inflammatory disease, or hypermobility-related instability.

MPM’s diagnosis-first approach helps determine whether pain is coming from one primary source or several overlapping contributors. This is especially important when pain travels into the leg, arm, ribs, hip, or pelvis, or when spine pain overlaps with autoimmune symptoms, morning stiffness, joint instability, or chronic pain sensitivity.

Request an Appointment

Diagnosis-first care

How MPM Approaches Spine Pain Evaluation

MPM uses a structured process to identify the source of spine pain and guide treatment planning.
  • 1

    Map the Pain Pattern

    MPM begins by understanding where the pain is located, where it travels, what triggers it, what relieves it, and how it affects walking, sitting, standing, sleep, work, and daily function. Radiating pain, numbness, tingling, weakness, stiffness, or inflammatory symptoms are reviewed carefully.
  • 2

    Review Imaging and Prior Care

    MRI, X-ray, CT, prior injection records, physical therapy notes, surgical history, and rheumatology or neurology workups may help clarify the pattern. MPM reviews imaging in context, because imaging findings do not always match the true pain generator.
  • 3

    Identify Mechanical, Nerve, SI Joint, or Inflammatory Drivers

    Spine pain may come from discs, nerves, facet joints, sacroiliac joints, muscles, ligaments, spinal stenosis, spondylosis, spondylolisthesis, inflammatory back pain, autoimmune disease, hypermobility-related instability, or chronic pain sensitization. MPM evaluates which drivers are most likely involved.
  • 4

    Build a Coordinated Treatment Plan

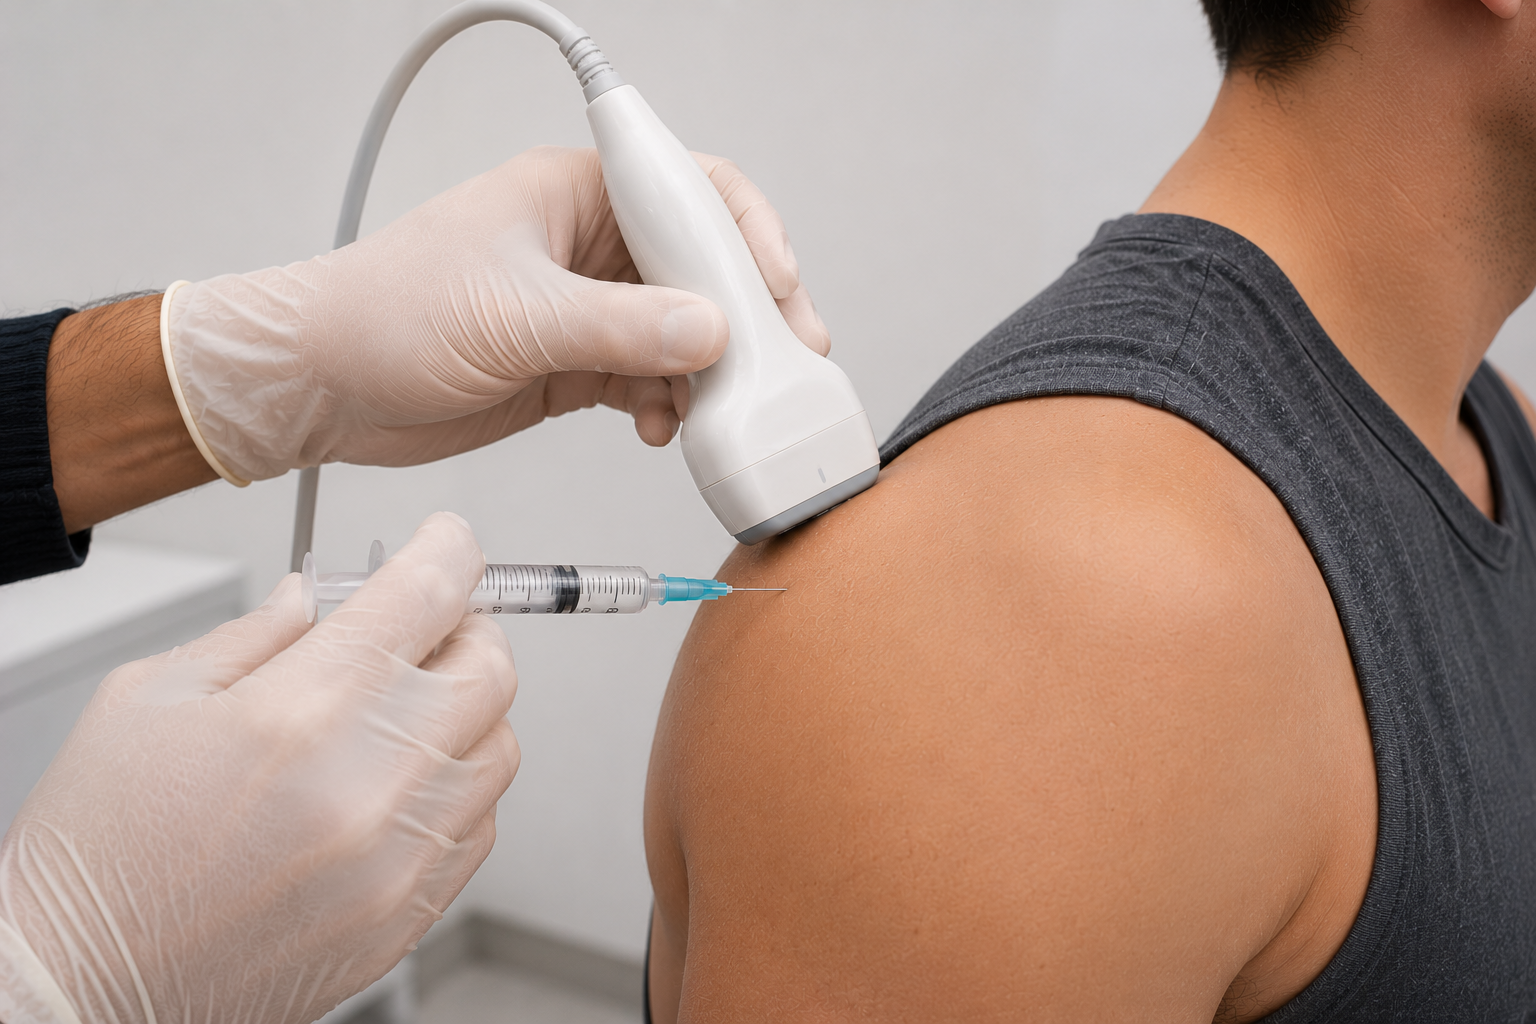
    Treatment may include medication management, physical rehabilitation coordination, acupuncture, Feldenkrais, biofeedback, pain psychology, diagnostic ultrasound when relevant, ultrasound-guided injections, epidural injections, spine injections, steroid injections, SI joint injections, regenerative options, neuromodulation, or referral to rheumatology, spine surgery, neurology, or rehabilitation when appropriate.

Spine Pain, Hypermobility, and Inflammation

Spine pain fits within MPM’s Musculoskeletal issues Zone of Expertise, with important overlap in Hypermobility and Autoimmune and Inflammatory care. Patients with EDS or hypermobility spectrum disorder may experience spine pain related to joint laxity, instability, muscle guarding, altered mechanics, recurrent sprains, or SI joint dysfunction.

Patients with autoimmune or inflammatory conditions may have pain that behaves differently from typical mechanical back pain. Morning stiffness, pain that improves with movement, SI joint inflammation, enthesitis, fatigue, or symptoms involving other joints may suggest an inflammatory pattern that requires rheumatology coordination.

MPM evaluates these patterns carefully so treatment is based on the likely source of pain, not assumptions.

PATIENT STORIES

Real Patients. Real Progress.

Hear from patients who came to Manhattan Pain Medicine looking for answers, clarity, and a more thoughtful path forward.
  • Michael O.

    5 star review

    These guys are the best. I've been going here for over 6 years and their familiarity with my Schwannomatosis (most ppl have never even heard of it - its rather rare) and their ability to diagnose my CRPS quickly and accurately and then treat it like I was merely getting a flu shot is just incredible...

    Google

  • John A.

    5 star review

    Highly recommended for those who need Pain Management. Everyone at Manhattan Pain Medicine is extremely nice and helpful. I have had very good interactions with both Dr. Siefferman and Dr. Louis. All of the staff is very responsive. 5 stars.

    Google

  • Rakhee K.

    5 star review

    The providers at Manhattan Pain Medicine are exceptional. I wish I had found them 30 years ago!

    Google

  • Annie R.

    5 star review

    I genuinely can’t say enough good things about the team at Manhattan Pain Medicine. I have MCAS, EDS, and an inflammatory autoimmune disease, and I’ve basically been searching for answers since I was a kid. I had years of unexplained inflammation markers, chronic pain, and allergic reactions despite...

    Google

  • Karine S.

    5 star review

    I have a complex medical history and have seen a lot of doctors over the years. Dr. Mikaberidze and Dr. Siefferman each took the time to really listen and understand everything I had been dealing with. I also appreciated how they work together and communicated about my care. I left with a plan that...

    Google

  • Edwin F-S.

    5 star review

    Sharing my gratitude for the pleasant experience last week during my visit, the medical team provided great care and also treated my session as a learning experience, I left my session with a wealth of knowledge. A big thank you to the kind, and professional staff who welcomed me to the office as a...

    Google

  • Madaline. M

    5 star review

    I cannot say enough good things about Manhattan Pain Medicine. From the moment I walked in, I felt truly cared for and taken seriously. Dr. Nino Mikaberidze, Director of Rheumatology, is exceptional — knowledgeable, compassionate, and incredibly thorough. She takes the time to listen, explains every...

    Google

  • Lauren W.

    5 star review

    Dr Siefferman is the most thorough, patient doctor I have even been to. Currently I travel from miami to nyc to see him because his bed side manner and desire to help is incomparable.

    ZocDoc

  • Dana S.

    5 star review

    This practice is wonderful. I have been a patient of Dr. Siefferman’s since 2019 and he’s extremely helpful and kind. He has brought in a Rheumatologist who is also great. They handle very complex pain issues and always try to find new ways to help me.

    Google

  • Frans M.

    5 star review

    Dr. Siefferman is an incredible doctor! He is extremely diligent and knowledgeable. It feels like you are his only patient. He invests a lot of time and effort into your injuries and concerns. I did not find these wonderful qualities with other pain specialists before, who were always rushed and som...

    ZocDoc

  • Gregory S.

    5 star review

    Dr. Siefferman is a doctor who combines the old world bedside manner of doctors from my childhood (60 years ago) with a sta te of the art embrace of modern technology. It is always a pleasure to have an appointment with him...always has options and solutions to my medical issues. He is truly the doc...

    ZocDoc

  • Judith R.

    5 star review

    Dr. Siefferman is a genius. He is very informed and listens attentively.

    ZocDoc

  • Joshua M.

    5 star review

    Dr. Siefferman and his entire team continue to be efficient, dedicated, and driven by precision and a genuine desire to give fantastic care. Will always recommend.

    ZocDoc

  • Michael W. S

    5 star review

    Doctor Siefferman is fantastic. Have been seeing him for 5 years. Couldn’t recommend more.

    ZocDoc

  • Stephanie G.

    5 star review

    Dr. Siefferman is the ONLY doctor who has ever been able to diagnose my pain and treat it. He is hands down the best

    ZocDoc

Spine Pain FAQs

Related conditions

Conditions That May Overlap With Spine Pain

Spine pain may overlap with sciatica and herniated discs, spinal stenosis, spondylosis, spondylolisthesis, sacroiliac joint dysfunction, facet-mediated back pain, inflammatory back pain, seronegative spondyloarthropathy, Sjogren’s, rheumatoid arthritis, arthritis joint pain, enthesitis, EDS, hypermobility spectrum disorder, thoracic outlet syndrome, scapular dyskinesia, slipping rib syndrome, and tethered cord.

Understanding Insurance Before You Begin

Before care begins, our team helps patients understand the practical side of treatment, including insurance verification, out-of-network benefits, cost-share estimates, self-pay options, and billing questions. We believe patients should have as much clarity as possible before moving forward.

Insurance & Billing

Request a Spine Pain Evaluation

If spine pain is affecting your movement, sleep, work, or daily life, MPM can help evaluate what may be contributing. Our diagnosis-first approach considers discs, nerves, facet joints, SI joints, muscles, inflammation, hypermobility, EDS, arthritis, and complex chronic pain patterns. Request an appointment to discuss your symptoms, prior imaging, and care options.

Request An Appointment

Insights & Research

Explore MPM Insights and Research, including patient-friendly articles, clinical perspectives, and research from our team to help explain how we understand complex pain, evaluate care options, and guide the path to treatment
Patient education

A Deeper Look at Spine Pain and Pain Generator Mapping

Spine pain can come from many different structures and systems, which is why treatment should begin with careful evaluation.

Spine Pain

Spine pain is one of the most common reasons patients seek care, but it is also one of the most commonly oversimplified. Pain in the neck, upper back, mid back, low back, or sacroiliac region can come from many different structures. It may involve discs, nerves, facet joints, sacroiliac joints, muscles, ligaments, inflammatory disease, hypermobility, spinal alignment, prior injury, or chronic pain mechanisms.

Some patients have pain that stays localized. Others have pain that travels into the arm, ribs, chest wall, hip, pelvis, buttock, or leg. Some describe burning, tingling, numbness, heaviness, weakness, stiffness, or sharp radiating pain. Others have pain that changes with sitting, standing, walking, bending, coughing, twisting, or lying down.

Why Diagnosis Matters Before Treatment

Spine pain treatment should not begin with a procedure or a generic exercise plan before the likely pain generator is understood. A herniated disc, spinal stenosis, facet joint irritation, SI joint dysfunction, muscle guarding, and inflammatory back pain can all feel like “back pain,” but they may require different treatment approaches.

Imaging can be useful, but it does not always tell the full story. Some patients have significant MRI findings that are not the main source of pain. Others have severe pain with relatively mild imaging changes. MPM reviews imaging in the context of the patient’s symptoms, examination, function, and prior treatment response.

Mechanical Spine Pain

Mechanical spine pain may come from muscles, ligaments, discs, joints, posture, movement patterns, arthritis, or structural changes. It may worsen with certain positions or activities and improve with rest, movement modification, strengthening, or targeted treatment. Common mechanical spine conditions include spondylosis, spondylolisthesis, facet arthropathy, disc-related pain, and sacroiliac joint dysfunction.

Mechanical pain can also be influenced by hip mechanics, pelvic alignment, thoracic mobility, scapular control, and lower extremity mechanics. This is why MPM evaluates the spine as part of a broader musculoskeletal system rather than one isolated body part.

Nerve-Related Spine Pain

Nerve-related spine pain can cause radiating symptoms, burning, tingling, numbness, electric pain, weakness, or pain that travels into the arm or leg. Sciatica and herniated discs are common examples. Spinal stenosis can also irritate or compress nerves, especially when walking or standing triggers leg symptoms.

Not all radiating pain comes from the spine. Peripheral nerve entrapment, neuropathy, thoracic outlet syndrome, piriformis syndrome, and pelvic nerve conditions can mimic spine-related nerve pain. MPM evaluates the nerve pathway carefully before recommending treatment.

Sacroiliac Joint Dysfunction and Spine-Like Pain

The sacroiliac joint can cause low back, buttock, hip, groin, pelvic, or leg-like pain. SI joint pain may be mistaken for lumbar spine pain, hip pain, or sciatica. It can be influenced by injury, pregnancy, altered mechanics, inflammatory disease, hypermobility, EDS, or prior spine surgery.

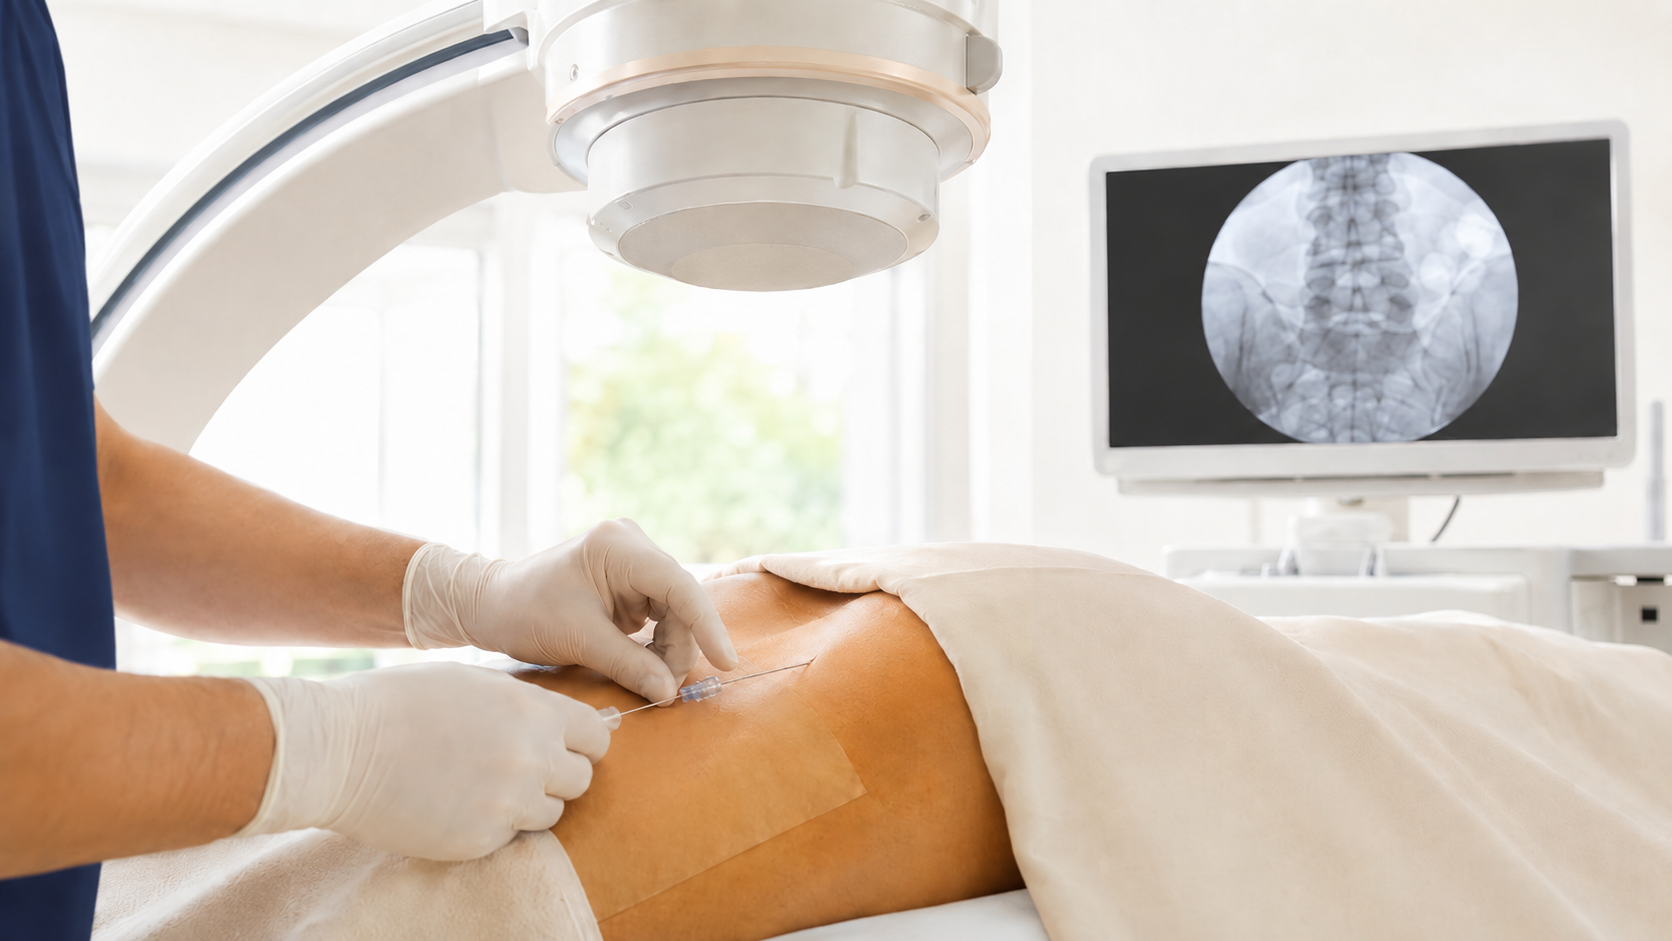
When SI joint dysfunction is suspected, MPM may evaluate movement, tenderness, provocative testing, imaging, and prior treatment response. In selected cases, sacroiliac joint injection may help clarify or treat the pain generator. For certain structural instability patterns, sacroiliac joint fixation or fusion may require specialist evaluation.

Inflammatory Back Pain and Autoimmune Overlap

Some spine pain is inflammatory rather than primarily mechanical. Inflammatory back pain may involve morning stiffness, improvement with movement, worsening with rest, sacroiliac pain, fatigue, enthesitis, and symptoms in other joints. Conditions such as seronegative spondyloarthropathy, rheumatoid arthritis, Sjogren’s, autoimmune-related pain, and arthritis-related joint pain may contribute to spine symptoms.

MPM does not replace rheumatology. Instead, MPM helps identify when pain may have an inflammatory pattern and coordinates with rheumatology when DMARDs, biologics, infusions, or immune-directed treatment may be appropriate. Pain-focused care may still be useful when inflammatory disease overlaps with mechanical pain, nerve pain, SI joint dysfunction, or chronic pain sensitization.

Hypermobility, EDS, and Spine Pain

Patients with EDS or hypermobility spectrum disorder may experience spine pain differently. Joint laxity, ligamentous instability, muscle guarding, recurrent sprains, altered proprioception, and SI joint dysfunction may contribute to pain. Some patients describe feeling unstable, overworked, or unable to tolerate aggressive stretching or manipulation.

Hypermobility-related spine pain should be evaluated carefully. The goal is not to assume every symptom is caused by EDS or HSD, but to understand whether joint instability, muscle compensation, nerve irritation, or altered mechanics are contributing.

Why Spine Pain Can Become Chronic

Spine pain can become chronic when the original pain generator persists, when several contributors overlap, or when the nervous system becomes more sensitive over time. Chronic spine pain may involve mechanical irritation, nerve pain, inflammation, muscle guarding, sleep disruption, fear of movement, stress physiology, and reduced activity tolerance.

Pain psychology, biofeedback, acupuncture, Feldenkrais, medication management, and rehabilitation coordination may support patients whose spine pain has become part of a broader chronic pain pattern. These approaches do not mean the pain is imagined. They help address how the nervous system, movement, and daily function interact with pain.

Treatment Options for Spine Pain

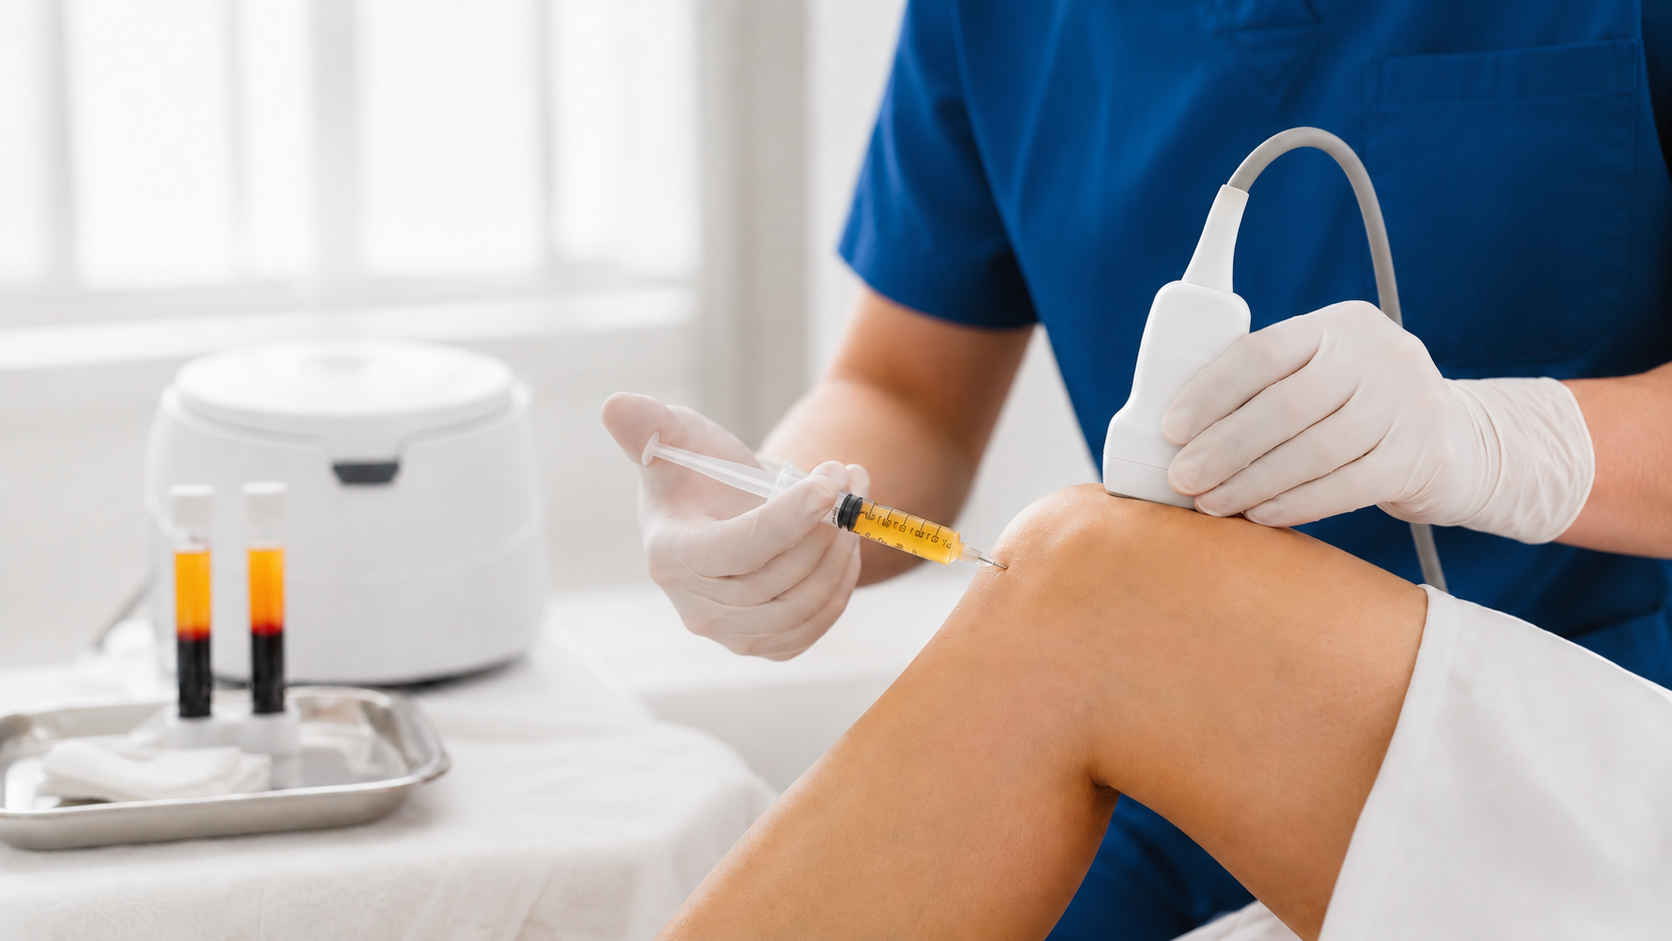
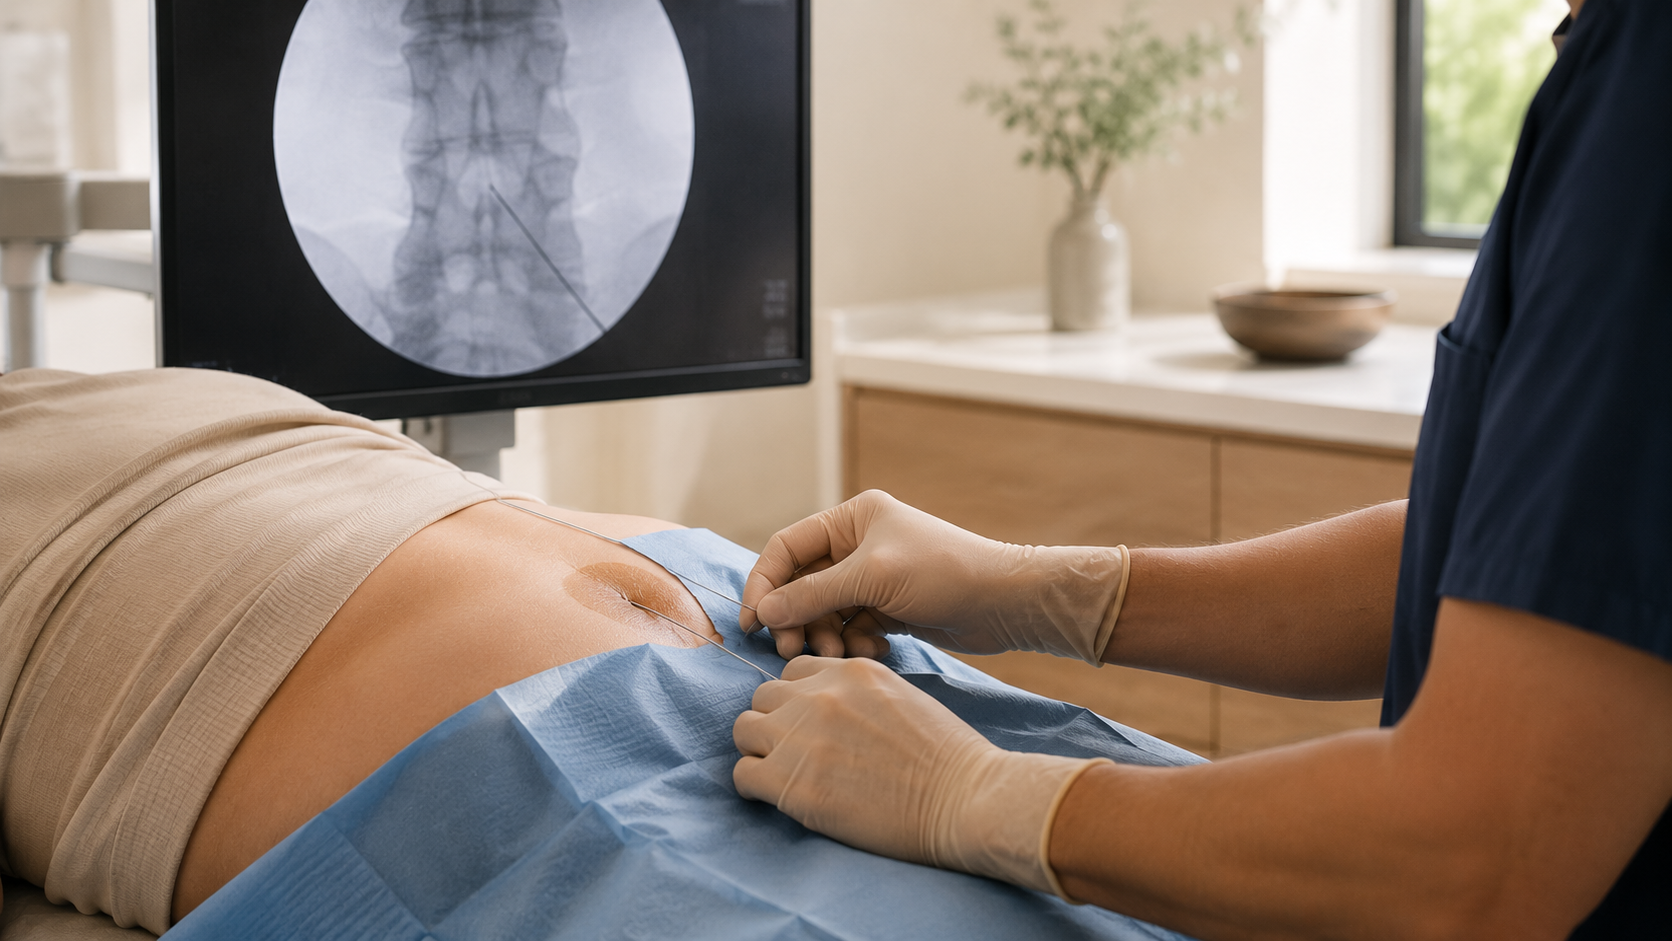
Treatment at MPM depends on the diagnosis and clinical pattern. Options may include medication management, physical rehabilitation coordination, acupuncture, Feldenkrais, weight-related support when relevant, biofeedback, pain psychology, diagnostic ultrasound when appropriate, ultrasound-guided injections, spine injections, epidural injections, epidural lysis of adhesions or Racz catheter procedures in selected cases, steroid injections, sacroiliac joint injection, regenerative medicine, PRP, prolotherapy, ketamine therapy, biologics or infusions through appropriate specialist coordination, spinal cord stimulation, dorsal root ganglion stimulation, and sacroiliac joint fixation or fusion referral when appropriate.

These treatments are not interchangeable. Epidural injections may be considered for selected nerve root pain patterns. SI joint injections may be considered when the SI joint is suspected as a pain generator. Neuromodulation may be considered for selected persistent neuropathic pain. Biologics and DMARDs belong to rheumatology-directed inflammatory disease care. Regenerative options require careful patient selection and should not be presented as universal spine treatments.
When Surgery May Be Considered

Some spine conditions require surgical evaluation, especially when there is progressive neurologic deficit, severe structural compression, instability, significant spinal stenosis, certain spondylolisthesis patterns, persistent disabling radicular pain, or failure of appropriate nonsurgical care. MPM can help evaluate pain generators and coordinate referral when surgical input is needed.

Pain medicine does not replace spine surgery when surgery is medically indicated. It can, however, help patients understand whether pain appears to be mechanical, nerve-related, inflammatory, SI joint-related, hypermobility-related, or mixed before moving forward with more invasive decisions.

When Spine Pain Requires Urgent Evaluation

Patients should seek urgent evaluation for spine pain associated with new weakness, progressive numbness, bowel or bladder dysfunction, saddle anesthesia, fever, unexplained weight loss, history of cancer, major trauma, severe night pain, chest pain, shortness of breath, sudden severe headache, or rapidly worsening symptoms.
These symptoms may indicate infection, fracture, malignancy, spinal cord compression, vascular conditions, neurologic disease, or other serious medical problems that require immediate attention.

How MPM Approaches Spine Pain Care

MPM approaches spine pain through a diagnosis-first model. The goal is to identify the source of pain, understand overlapping contributors, interpret imaging carefully, and build a treatment plan that fits the patient’s symptoms, goals, and risk profile.

For patients looking for spine pain treatment in Manhattan or NYC, MPM provides coordinated pain medicine care for back pain, neck pain, sciatica, herniated discs, spinal stenosis, spondylosis, spondylolisthesis, SI joint pain, inflammatory back pain, hypermobility-related spine pain, and complex chronic pain patterns.