Cluster Headache Evaluation and Treatment in Manhattan

Cluster headache can cause extremely severe, recurring one-sided headache attacks, often around the eye, temple, or forehead, with eye tearing, redness, nasal congestion, eyelid changes, sweating, or restlessness.

Related Zones of Expertise

Severe, one-sided headaches can be a sign of cluster headaches. Dr. Siefferman discusses how they're diagnosed and the treatment options available to help reduce attacks and improve quality of life.

Understanding Cluster Headache

Cluster headache is a severe trigeminal autonomic headache disorder that causes repeated attacks of intense one-sided head pain, most often around the eye, temple, forehead, or upper face. Attacks may occur with autonomic symptoms on the same side, such as eye tearing, eye redness, nasal congestion, runny nose, eyelid swelling, facial sweating, pupil changes, eyelid drooping, or restlessness.

Cluster headache attacks often come in cycles. Some patients experience attacks at the same time each day or night, and attacks may recur over weeks or months before improving. Because cluster headache can resemble migraine, sinus headache, trigeminal neuralgia, hemicrania, dental pain, eye pain, or other headache disorders, accurate diagnosis is essential.

At Manhattan Pain Medicine (MPM), evaluation begins by confirming the headache pattern, attack duration, triggers, autonomic symptoms, prior treatment response, and red flags. The goal is to determine whether symptoms fit cluster headache or another headache or facial pain condition before building a treatment plan.

Specialist Care for Severe One-Sided Headache Attacks

For patients looking for cluster headache treatment in Manhattan, MPM evaluates the full headache pattern, including pain location, timing, attack duration, frequency, side-locked symptoms, eye and nasal symptoms, restlessness, prior imaging, medication use, and response to acute or preventive treatments.

Care may include medication management, coordination for fast-acting acute treatment, preventive planning, selected nerve-targeted procedures when appropriate, pain psychology, biofeedback, acupuncture, and referral coordination with neurology, ophthalmology, ENT, emergency care, or other specialists when needed.

MPM does not assume that every severe one-sided headache is cluster headache. The evaluation also considers migraine, hemicrania, trigeminal autonomic cephalalgia, trigeminal neuralgia, sinus disease, dental causes, TMJ disorders, eye conditions, cervical referral, and other neurologic or medical causes.

Why Cluster Headache Is Often Misdiagnosed

Cluster headache may be mistaken for migraine, sinus headache, dental pain, eye pain, trigeminal neuralgia, or stress-related headache because the pain can be intense, one-sided, and centered around the eye, temple, forehead, upper jaw, or face.

The timing and associated symptoms are important. Cluster headache attacks often last 15 to 180 minutes when untreated and may occur repeatedly during a cluster period. Eye tearing, redness, nasal congestion, runny nose, eyelid changes, facial sweating, pupil changes, and restlessness help distinguish cluster headache from other headache disorders.

MPM’s diagnosis-first approach is designed to identify the correct headache type, review prior treatment response, and determine which acute, preventive, interventional, or specialty care options may be appropriate.

Request an Appointment

Diagnosis-first care

How MPM Approaches Cluster Headache Evaluation

MPM evaluates severe one-sided headache attacks by reviewing timing, attack duration, autonomic symptoms, restlessness, prior treatment response, and red flags before recommending care.
  • 1

    Confirm the Headache Pattern

    MPM reviews where the pain occurs, how long attacks last, how often they happen, whether they occur at predictable times, and whether symptoms appear in cycles. Severe one-sided pain around the eye, temple, or forehead with repeated attacks may suggest cluster headache.
  • 2

    Identify Autonomic Symptoms

    Cluster headache often includes symptoms on the same side as the pain, such as eye tearing, red eye, nasal congestion, runny nose, eyelid swelling, facial sweating, pupil changes, eyelid drooping, or marked restlessness. These features help distinguish cluster headache from migraine, sinus headache, and other headache disorders.
  • 3

    Rule Out Similar Conditions

    MPM considers migraine, hemicrania, trigeminal autonomic cephalalgias, trigeminal neuralgia, sinus disease, TMJ disorders, dental pain, eye conditions, cervical referral, and other neurologic causes. Imaging, neurology evaluation, ophthalmology, ENT, or emergency evaluation may be needed when symptoms are new, atypical, severe, or changing.
  • 4

    Build an Acute and Preventive Care Plan

    Treatment may include medication management, coordination for fast-acting acute therapies, preventive medication planning, selected nerve blocks, pain psychology, biofeedback, acupuncture, and referral coordination. The plan depends on the diagnosis, attack frequency, medical history, medication risks, prior response, and urgency of symptoms.

Cluster Headache and Autonomic Symptoms

Cluster headache fits within MPM’s Headache Zone of Expertise, with important overlap in Autonomic dysfunction because cluster headache includes autonomic symptoms such as eye tearing, red eye, nasal congestion, runny nose, eyelid swelling, sweating, pupil changes, and restlessness.

These symptoms are not simply allergy or sinus symptoms when they occur with severe, recurring, one-sided headache attacks. They may reflect trigeminal autonomic pathway activation.

MPM evaluates these symptoms in context, including timing, laterality, attack duration, medication response, and overlap with migraine, hemicrania, TACs, trigeminal neuralgia, or other headache disorders.

PATIENT STORIES

Real Patients. Real Progress.

Hear from patients who came to Manhattan Pain Medicine looking for answers, clarity, and a more thoughtful path forward.
  • Michael O.

    5 star review

    These guys are the best. I've been going here for over 6 years and their familiarity with my Schwannomatosis (most ppl have never even heard of it - its rather rare) and their ability to diagnose my CRPS quickly and accurately and then treat it like I was merely getting a flu shot is just incredible...

    Google

  • John A.

    5 star review

    Highly recommended for those who need Pain Management. Everyone at Manhattan Pain Medicine is extremely nice and helpful. I have had very good interactions with both Dr. Siefferman and Dr. Louis. All of the staff is very responsive. 5 stars.

    Google

  • Rakhee K.

    5 star review

    The providers at Manhattan Pain Medicine are exceptional. I wish I had found them 30 years ago!

    Google

  • Annie R.

    5 star review

    I genuinely can’t say enough good things about the team at Manhattan Pain Medicine. I have MCAS, EDS, and an inflammatory autoimmune disease, and I’ve basically been searching for answers since I was a kid. I had years of unexplained inflammation markers, chronic pain, and allergic reactions despite...

    Google

  • Karine S.

    5 star review

    I have a complex medical history and have seen a lot of doctors over the years. Dr. Mikaberidze and Dr. Siefferman each took the time to really listen and understand everything I had been dealing with. I also appreciated how they work together and communicated about my care. I left with a plan that...

    Google

  • Edwin F-S.

    5 star review

    Sharing my gratitude for the pleasant experience last week during my visit, the medical team provided great care and also treated my session as a learning experience, I left my session with a wealth of knowledge. A big thank you to the kind, and professional staff who welcomed me to the office as a...

    Google

  • Madaline. M

    5 star review

    I cannot say enough good things about Manhattan Pain Medicine. From the moment I walked in, I felt truly cared for and taken seriously. Dr. Nino Mikaberidze, Director of Rheumatology, is exceptional — knowledgeable, compassionate, and incredibly thorough. She takes the time to listen, explains every...

    Google

  • Lauren W.

    5 star review

    Dr Siefferman is the most thorough, patient doctor I have even been to. Currently I travel from miami to nyc to see him because his bed side manner and desire to help is incomparable.

    ZocDoc

  • Dana S.

    5 star review

    This practice is wonderful. I have been a patient of Dr. Siefferman’s since 2019 and he’s extremely helpful and kind. He has brought in a Rheumatologist who is also great. They handle very complex pain issues and always try to find new ways to help me.

    Google

  • Frans M.

    5 star review

    Dr. Siefferman is an incredible doctor! He is extremely diligent and knowledgeable. It feels like you are his only patient. He invests a lot of time and effort into your injuries and concerns. I did not find these wonderful qualities with other pain specialists before, who were always rushed and som...

    ZocDoc

  • Gregory S.

    5 star review

    Dr. Siefferman is a doctor who combines the old world bedside manner of doctors from my childhood (60 years ago) with a sta te of the art embrace of modern technology. It is always a pleasure to have an appointment with him...always has options and solutions to my medical issues. He is truly the doc...

    ZocDoc

  • Judith R.

    5 star review

    Dr. Siefferman is a genius. He is very informed and listens attentively.

    ZocDoc

  • Joshua M.

    5 star review

    Dr. Siefferman and his entire team continue to be efficient, dedicated, and driven by precision and a genuine desire to give fantastic care. Will always recommend.

    ZocDoc

  • Michael W. S

    5 star review

    Doctor Siefferman is fantastic. Have been seeing him for 5 years. Couldn’t recommend more.

    ZocDoc

  • Stephanie G.

    5 star review

    Dr. Siefferman is the ONLY doctor who has ever been able to diagnose my pain and treat it. He is hands down the best

    ZocDoc

Cluster Headache FAQs

Related conditions

Conditions That May Overlap With Cluster Headache

Cluster headache may overlap with headache and migraine, chronic migraine, hemicrania, tension headache, trigeminal autonomic cephalalgia, trigeminal neuralgia, TMJ disorders, cervical dystonia, orofacial dystonia, autonomic dysfunction, and complex chronic pain.

Understanding Insurance Before You Begin

Before care begins, our team helps patients understand the practical side of treatment, including insurance verification, out-of-network benefits, cost-share estimates, self-pay options, and billing questions. We believe patients should have as much clarity as possible before moving forward.

Insurance & Billing

Request a Cluster Headache Evaluation

If you are experiencing severe one-sided headache attacks around the eye, temple, or forehead, especially with eye tearing, redness, nasal congestion, eyelid changes, sweating, or restlessness, MPM can help evaluate what may be contributing. Our diagnosis-first approach considers cluster headache, migraine, hemicrania, trigeminal autonomic cephalalgias, trigeminal neuralgia, sinus-related pain, TMJ disorders, and other headache or facial pain conditions. Request an appointment to discuss your symptoms and care options.

Request An Appointment

Insights & Research

Explore MPM Insights and Research, including patient-friendly articles, clinical perspectives, and research from our team to help explain how we understand complex pain, evaluate care options, and guide the path to treatment
Patient education

A Deeper Look at Cluster Headache and Trigeminal Autonomic Headache Disorders

Cluster headache is a severe headache disorder that can cause repeated one-sided attacks with eye, nasal, facial, and autonomic symptoms.

Cluster Headache

Cluster headache is one of the most severe primary headache disorders. It usually causes intense one-sided pain around the eye, temple, forehead, or upper face. Attacks may feel piercing, burning, stabbing, or unbearable, and many patients feel restless or agitated during an attack.

Cluster headache is part of a group of headache disorders called trigeminal autonomic cephalalgias, or TACs. These conditions involve head pain along with autonomic symptoms, often on the same side as the pain. In cluster headache, those symptoms may include eye tearing, red eye, nasal congestion, runny nose, eyelid swelling, facial sweating, pupil changes, eyelid drooping, or facial flushing.

Why Cluster Headache Can Be Missed

Cluster headache can be misdiagnosed because its symptoms overlap with other conditions. Eye pain may be mistaken for an eye problem. Nasal congestion may be mistaken for sinus headache. Jaw or facial pain may be mistaken for dental pain, TMJ disorder, or trigeminal neuralgia. Severe head pain may be treated as migraine even when the timing and autonomic symptoms suggest another pattern.

The details matter. Cluster headache attacks are usually one-sided, severe or very severe, and relatively short compared with many migraine attacks. They often last 15 to 180 minutes when untreated and may happen repeatedly during a cluster period. Some patients have attacks at the same time each day or night.

At MPM, evaluation begins with the attack pattern. The team reviews where the pain occurs, whether it stays on one side, how long attacks last, how often they happen, whether there are eye or nasal symptoms, whether the patient feels restless, and what treatments have or have not helped.

Cluster Headache vs. Migraine

Cluster headache and migraine can both cause severe head pain, but they often behave differently. Migraine may last hours to days and may include nausea, vomiting, light sensitivity, sound sensitivity, aura, and worsening with activity. Many migraine patients want to lie still in a quiet, dark room.

Cluster headache attacks are often shorter, more frequent, and strongly one-sided. They commonly include autonomic symptoms such as tearing, red eye, nasal congestion, runny nose, eyelid changes, sweating, or pupil changes. Patients often feel restless and may pace, rock, or feel unable to remain still.

Some patients have overlapping features, which is why diagnosis should be based on the full headache pattern rather than one symptom alone.

Cluster Headache vs. Hemicrania and Other TACs

Cluster headache is one type of trigeminal autonomic cephalalgia. Other TACs include conditions such as hemicrania and other rare headache syndromes. These disorders can also cause one-sided pain with autonomic symptoms, but the attack duration, frequency, medication response, and diagnostic criteria may differ.

Hemicrania, for example, may respond very specifically to certain medication trials under clinician supervision. Trigeminal neuralgia may cause brief electric facial pain triggered by touch, chewing, brushing teeth, or talking. Sinus headache may involve congestion and facial pressure but usually follows a different clinical pattern.

MPM evaluates these differences carefully to help guide the correct treatment pathway.

Why Cluster Headaches Happen in Cycles

Many patients with cluster headache experience attacks in cycles. A cluster period may last weeks or months, followed by a remission period. Others have chronic cluster headache with limited remission. Some attacks occur at predictable times, including during sleep.

This timing pattern is one reason cluster headache is thought to involve brain timing mechanisms and trigeminal-autonomic pathways. For patients, the pattern can feel alarming and exhausting because they may anticipate attacks at the same time each day or night.

Treatment planning should account for both acute attacks and prevention during cluster periods.

Treatment Options for Cluster Headache

Cluster headache treatment often includes acute strategies and preventive strategies. Acute treatment is designed to stop or reduce an attack quickly. Because cluster headache attacks peak quickly, fast-acting treatments are often more appropriate than slower oral medications for stopping individual attacks.

Acute options may include oxygen therapy coordination when appropriate, injectable or nasal triptans for selected patients, and other clinician-guided strategies. These treatments require medical supervision and may not be appropriate for every patient, especially when cardiovascular risks or other contraindications are present.

Preventive treatment is used to reduce attack frequency during a cluster period or manage chronic cluster headache. Medication management may include preventive medications selected based on the patient’s diagnosis, medical history, risk profile, and prior response.

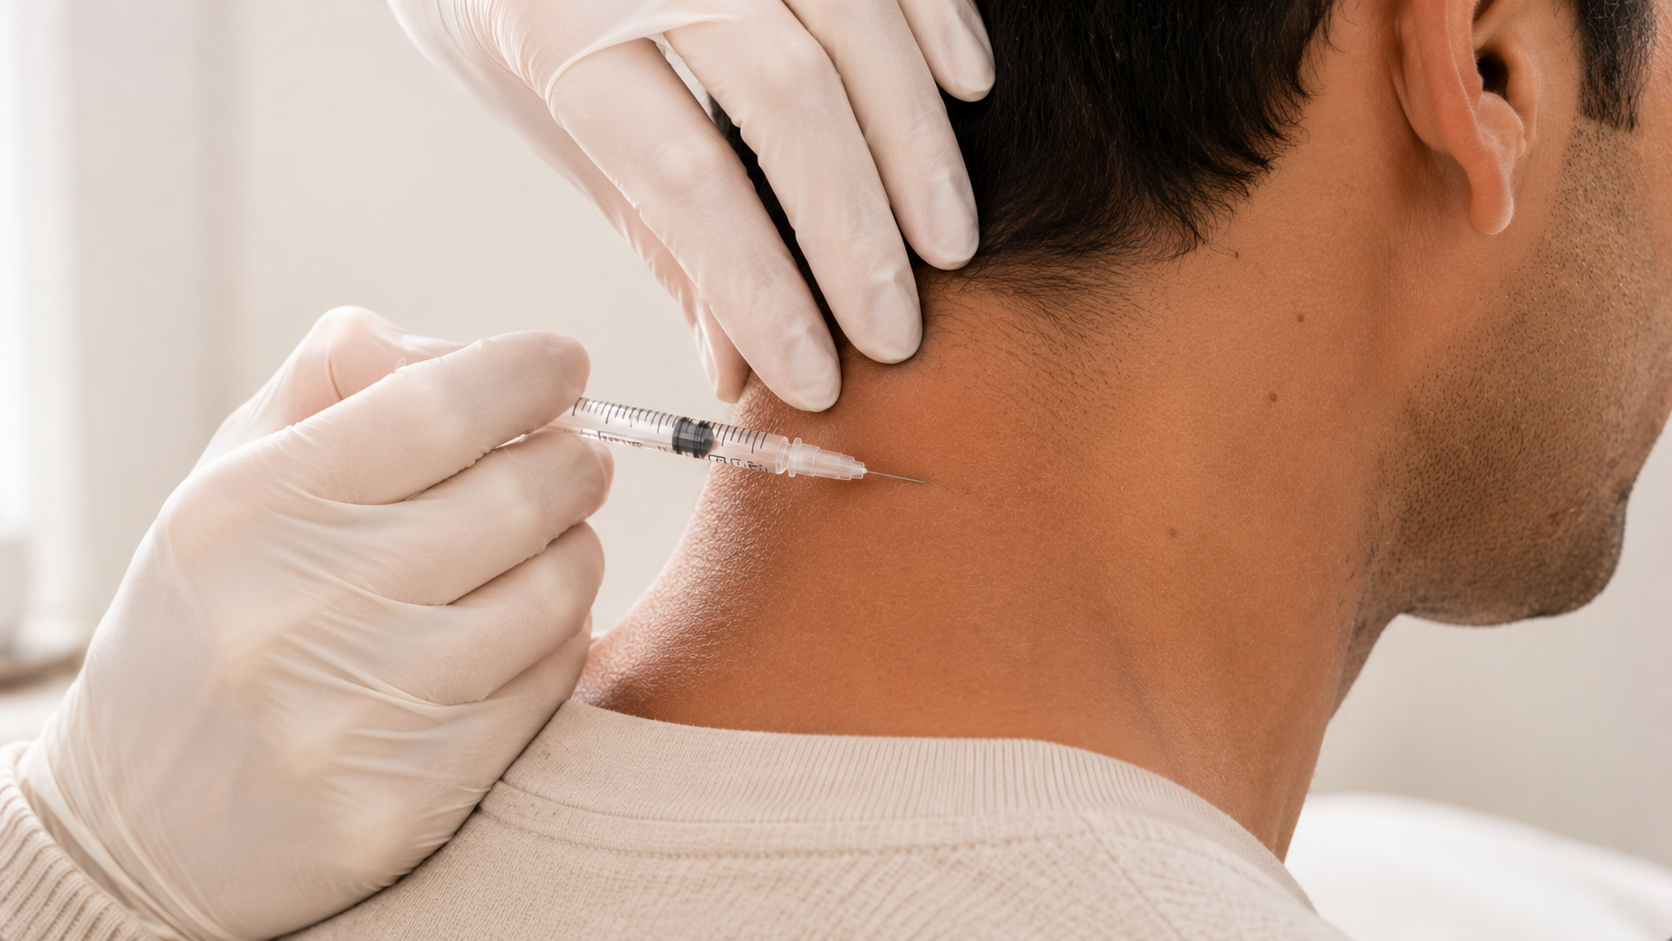
Selected nerve-targeted procedures may be considered when the headache pattern supports them. These may include occipital nerve blocks, trigeminal nerve-related approaches, or sphenopalatine ganglion region approaches in carefully selected cases. These procedures are not universal cluster headache treatments and should be considered only after diagnosis and risk review.

The Role of Pain Psychology and Biofeedback

Cluster headache is not psychological. The pain is real, neurologic, and often intensely disabling. However, pain psychology and biofeedback may help some patients manage the fear, sleep disruption, stress physiology, functional impact, and anticipatory anxiety that can develop when attacks are severe and recurring.

These therapies do not replace medical headache treatment. They may support coping, nervous system regulation, pacing, and quality of life as part of a broader care plan.

When Imaging or Specialty Care May Be Needed

Cluster headache diagnosis is based on the headache pattern and clinical evaluation, but imaging or specialist referral may be needed when symptoms are new, unusual, atypical, progressively worsening, or associated with neurologic signs. Neurology, ophthalmology, ENT, dentistry, emergency care, or other specialists may be involved depending on the symptoms.

MPM coordinates care when severe headache may require additional evaluation, when standard treatments have not worked, or when the diagnosis is unclear.

When Severe Headache Requires Urgent Evaluation

Patients should seek urgent evaluation for sudden explosive headache, the worst headache of their life, headache with weakness, numbness, confusion, fainting, seizure, fever, stiff neck, vision loss, head injury, cancer history, immune suppression, pregnancy, new headache later in life, or a major change in headache pattern.

Even when someone has a known headache disorder, a new or different headache pattern should be taken seriously.

How MPM Approaches Cluster Headache Care

MPM approaches cluster headache through a diagnosis-first, coordinated model. The goal is to confirm whether the pattern fits cluster headache, identify autonomic features, distinguish cluster headache from migraine, sinus headache, hemicrania, trigeminal neuralgia, TMJ disorders, and other facial pain conditions, and build a treatment plan that fits the patient’s attack pattern and medical history.

For patients looking for cluster headache treatment in Manhattan, MPM offers a careful headache and pain medicine perspective focused on accurate diagnosis, medication management, selected interventional options, supportive care, and referral coordination when needed.

The goal is to clarify the headache type and guide appropriate next steps without overpromising outcomes.