Hernia Pain Treatment in Manhattan and NYC

Hernia-related pain can cause abdominal, groin, pelvic, upper thigh, or hip-region symptoms, and may overlap with nerve entrapment, abdominal wall pain, pelvic floor dysfunction, sports hernia, or pain after hernia repair.

Related Zones of Expertise

Learn how Dr. Siefferman evaluates hernia-related pain, identifies its underlying cause, and develops personalized treatment plans to help patients find lasting relief.

Understanding Hernia Pain

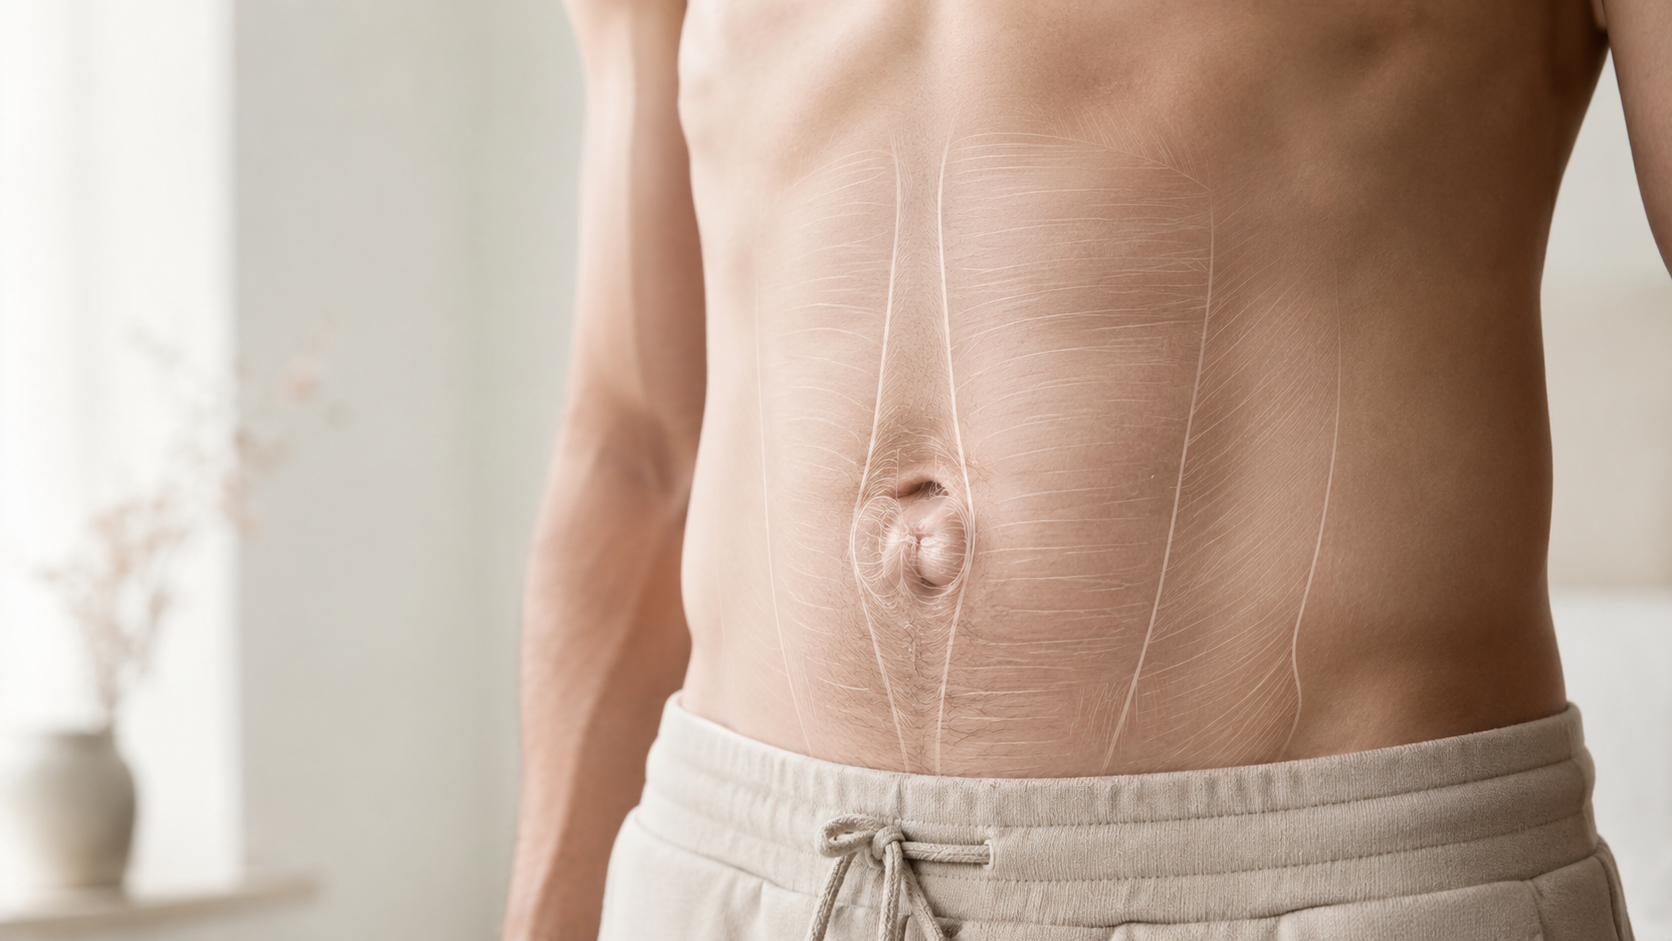
Hernia pain can occur when tissue pushes through a weakened area in the abdominal wall, groin, or pelvic region. Some hernias cause a visible bulge, pressure, aching, pulling, sharp pain, or pain that worsens with coughing, lifting, standing, straining, exercise, or core activity. Other hernia-like pain patterns may occur without an obvious bulge, especially when the source is nerve irritation, abdominal wall pain, pelvic floor dysfunction, athletic pubalgia, scar tissue, or pain after prior hernia repair.

At Manhattan Pain Medicine (MPM), evaluation begins by identifying whether pain is likely coming from a true hernia, post-hernia repair nerve irritation, abdominal wall nerve entrapment, ACNES, pelvic floor dysfunction, sports hernia or athletic pubalgia, femoral hernia, obturator hernia, umbilical hernia, endometriosis, hip or pelvic mechanics, peripheral nerve entrapment, or another pain generator.

MPM does not replace surgical evaluation when a hernia may require repair. Our role is strongest when pain is chronic, post-surgical, nerve-related, pelvic-region, abdominal wall-related, or diagnostically unclear.

Specialist Care for Hernia-Related and Groin Pain

MPM evaluates hernia-related pain by reviewing the pain location, triggers, prior imaging, surgical history, activity pattern, pelvic symptoms, abdominal wall tenderness, nerve distribution, scar or mesh-related concerns, and musculoskeletal contributors.

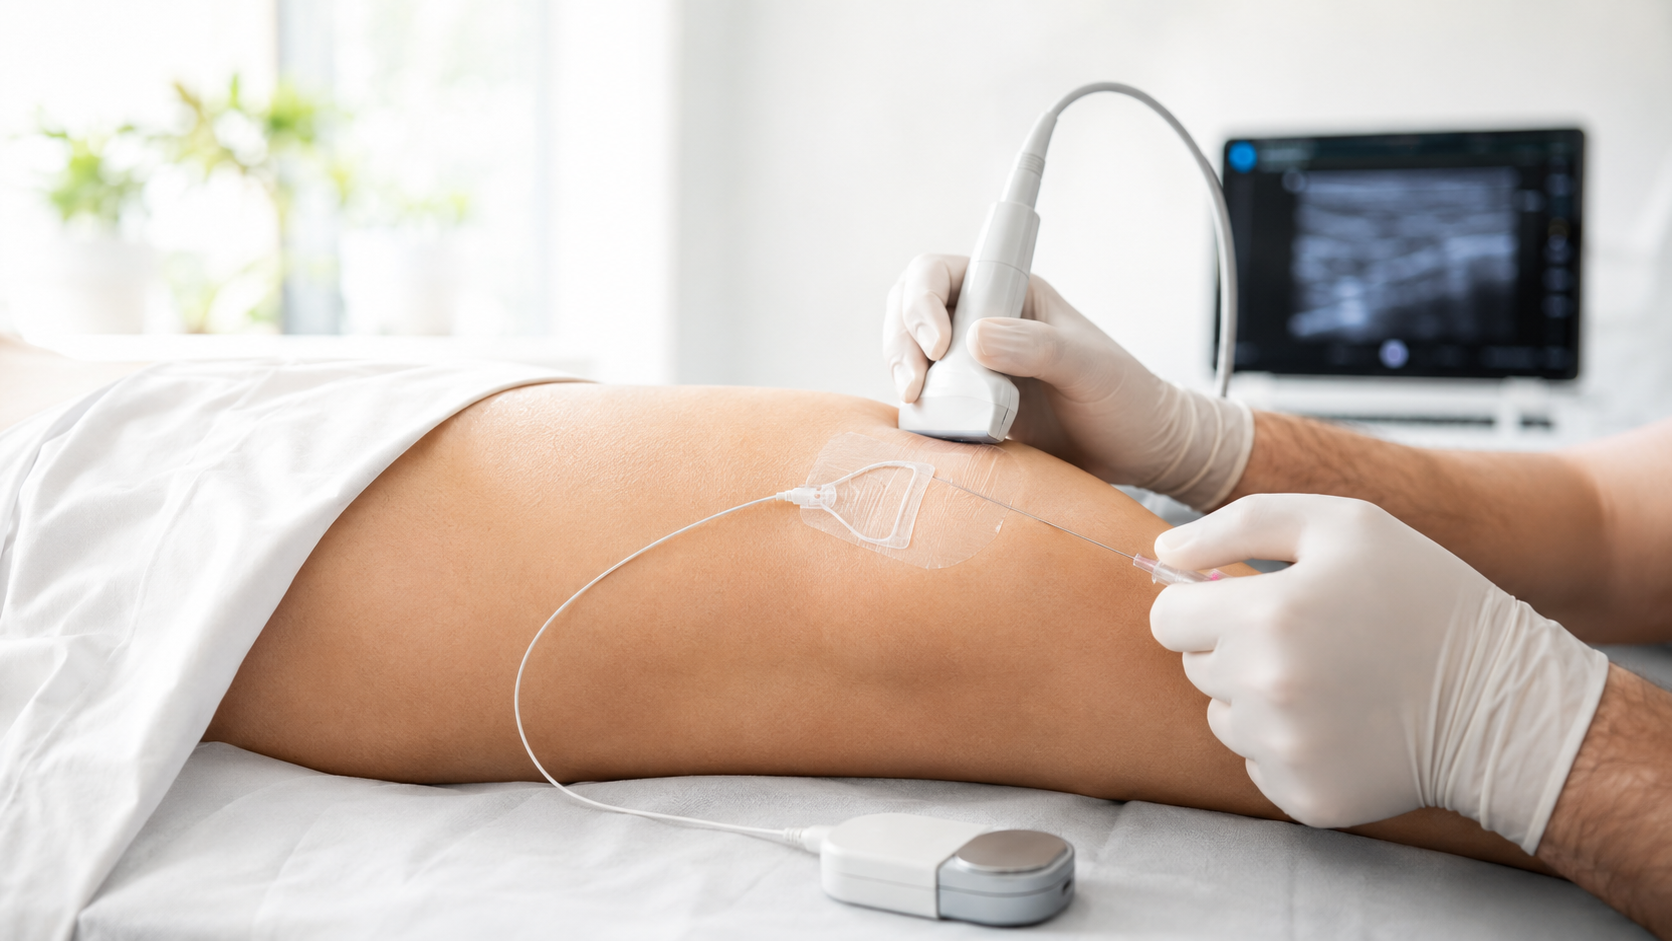
For patients looking for hernia pain treatment in NYC, MPM’s diagnosis-first approach helps determine whether symptoms require surgical evaluation, pain medicine care, pelvic pain evaluation, nerve-focused treatment, or coordinated care across several specialties. Treatment may include diagnostic ultrasound when appropriate, ultrasound-guided injections, steroid injections in selected cases, nerve hydrodissection only when anatomically and clinically appropriate, peripheral nerve stimulation for selected chronic nerve pain patterns, acupuncture, and coordination with general surgery, pelvic specialists, orthopedics, gynecology, urology, gastroenterology, or physical therapy when needed.

Why Hernia Pain Can Be Difficult to Diagnose

Hernia-like pain can be difficult to diagnose because groin, abdominal, pelvic, hip-region, and upper thigh pain can come from many overlapping sources. A true hernia may cause pain, pressure, or a bulge, but similar symptoms can also come from abdominal wall nerve entrapment, ACNES, pelvic floor dysfunction, athletic pubalgia, peripheral nerve entrapment, endometriosis, hip pathology, abdominal wall strain, pelvic mechanics, spine-related pain, scar tissue, mesh-related irritation, or post-surgical nerve pain.

MPM’s diagnosis-first approach is designed to avoid assuming that every groin or abdominal wall pain pattern is caused by a hernia. The evaluation considers whether the pain pattern suggests a structural hernia that needs surgical input, a nerve-related pain generator, a pelvic floor or musculoskeletal contributor, or a mixed pain pattern requiring coordinated care.

Request an Appointment

Diagnosis-first care

How MPM Approaches Hernia Pain Evaluation

MPM evaluates abdominal, groin, pelvic, and post-hernia repair pain by identifying the likely pain generator before recommending treatment.
  • 1

    Map the Pain Location and Triggers

    MPM begins by reviewing where the pain occurs, whether there is a bulge, and what worsens symptoms. Pain that increases with coughing, lifting, straining, standing, exercise, core activity, or pressure may suggest a structural, abdominal wall, or groin-related source.
  • 2

    Review Hernia and Surgical History

    For patients with a known hernia or prior hernia repair, MPM reviews the type of hernia, surgical history, mesh or scar-related concerns, imaging, recovery timeline, and whether symptoms are new, persistent, recurrent, or changed after surgery.
  • 3

    Differentiate Nerve, Pelvic, and Musculoskeletal Contributors

    Hernia-like pain can overlap with ACNES, abdominal wall nerve entrapment, peripheral nerve entrapment, pelvic floor dysfunction, endometriosis, athletic pubalgia, hip pathology, anterior pelvic tilt, and hypermobility-related mechanics. MPM evaluates these possibilities before treatment is selected.
  • 4

    Coordinate the Right Care Pathway

    If symptoms suggest a surgically significant hernia, MPM coordinates referral to general surgery or the appropriate specialist. If symptoms suggest nerve-related, post-surgical, abdominal wall, pelvic, or musculoskeletal pain, care may include diagnostic ultrasound, ultrasound-guided injections, selected nerve-focused procedures, acupuncture, or coordinated pelvic and musculoskeletal care.

Hernia Pain, Hypermobility, and Pelvic Mechanics

Hernia pain fits within MPM’s Pelvic Pain and Hypermobility Zones of Expertise when symptoms involve groin pain, pelvic-region pain, abdominal wall pain, pelvic floor dysfunction, connective tissue laxity, or altered mechanics through the hips, pelvis, and core.

In patients with hypermobility spectrum disorder or Ehlers-Danlos syndrome, connective tissue laxity, joint instability, pelvic mechanics, and abdominal wall vulnerability may complicate pain patterns. MPM evaluates these relationships carefully without assuming that hypermobility is the cause of every hernia-like symptom.

Treatments Related to Hernia Pain

Treatment depends on whether pain is driven by a true hernia, post-surgical nerve irritation, abdominal wall nerve entrapment, scar tissue, pelvic floor dysfunction, athletic pubalgia, peripheral nerve irritation, or another overlapping pain generator.
PATIENT STORIES

Real Patients. Real Progress.

Hear from patients who came to Manhattan Pain Medicine looking for answers, clarity, and a more thoughtful path forward.
  • Michael O.

    5 star review

    These guys are the best. I've been going here for over 6 years and their familiarity with my Schwannomatosis (most ppl have never even heard of it - its rather rare) and their ability to diagnose my CRPS quickly and accurately and then treat it like I was merely getting a flu shot is just incredible...

    Google

  • John A.

    5 star review

    Highly recommended for those who need Pain Management. Everyone at Manhattan Pain Medicine is extremely nice and helpful. I have had very good interactions with both Dr. Siefferman and Dr. Louis. All of the staff is very responsive. 5 stars.

    Google

  • Rakhee K.

    5 star review

    The providers at Manhattan Pain Medicine are exceptional. I wish I had found them 30 years ago!

    Google

  • Annie R.

    5 star review

    I genuinely can’t say enough good things about the team at Manhattan Pain Medicine. I have MCAS, EDS, and an inflammatory autoimmune disease, and I’ve basically been searching for answers since I was a kid. I had years of unexplained inflammation markers, chronic pain, and allergic reactions despite...

    Google

  • Karine S.

    5 star review

    I have a complex medical history and have seen a lot of doctors over the years. Dr. Mikaberidze and Dr. Siefferman each took the time to really listen and understand everything I had been dealing with. I also appreciated how they work together and communicated about my care. I left with a plan that...

    Google

  • Edwin F-S.

    5 star review

    Sharing my gratitude for the pleasant experience last week during my visit, the medical team provided great care and also treated my session as a learning experience, I left my session with a wealth of knowledge. A big thank you to the kind, and professional staff who welcomed me to the office as a...

    Google

  • Madaline. M

    5 star review

    I cannot say enough good things about Manhattan Pain Medicine. From the moment I walked in, I felt truly cared for and taken seriously. Dr. Nino Mikaberidze, Director of Rheumatology, is exceptional — knowledgeable, compassionate, and incredibly thorough. She takes the time to listen, explains every...

    Google

  • Lauren W.

    5 star review

    Dr Siefferman is the most thorough, patient doctor I have even been to. Currently I travel from miami to nyc to see him because his bed side manner and desire to help is incomparable.

    ZocDoc

  • Dana S.

    5 star review

    This practice is wonderful. I have been a patient of Dr. Siefferman’s since 2019 and he’s extremely helpful and kind. He has brought in a Rheumatologist who is also great. They handle very complex pain issues and always try to find new ways to help me.

    Google

  • Frans M.

    5 star review

    Dr. Siefferman is an incredible doctor! He is extremely diligent and knowledgeable. It feels like you are his only patient. He invests a lot of time and effort into your injuries and concerns. I did not find these wonderful qualities with other pain specialists before, who were always rushed and som...

    ZocDoc

  • Gregory S.

    5 star review

    Dr. Siefferman is a doctor who combines the old world bedside manner of doctors from my childhood (60 years ago) with a sta te of the art embrace of modern technology. It is always a pleasure to have an appointment with him...always has options and solutions to my medical issues. He is truly the doc...

    ZocDoc

  • Judith R.

    5 star review

    Dr. Siefferman is a genius. He is very informed and listens attentively.

    ZocDoc

  • Joshua M.

    5 star review

    Dr. Siefferman and his entire team continue to be efficient, dedicated, and driven by precision and a genuine desire to give fantastic care. Will always recommend.

    ZocDoc

  • Michael W. S

    5 star review

    Doctor Siefferman is fantastic. Have been seeing him for 5 years. Couldn’t recommend more.

    ZocDoc

  • Stephanie G.

    5 star review

    Dr. Siefferman is the ONLY doctor who has ever been able to diagnose my pain and treat it. He is hands down the best

    ZocDoc

Hernia Pain FAQs

Related conditions

Conditions That May Overlap With Hernia Pain

Hernia-related pain may overlap with abdominal pain, ACNES, peripheral nerve entrapment, pelvic pain, pelvic floor dysfunction, anterior pelvic tilt, Ehlers-Danlos syndrome, hypermobility spectrum disorder, endometriosis, obturator hernia, femoral hernia, sports hernia or athletic pubalgia, and umbilical hernia.

Understanding Insurance Before You Begin

Before care begins, our team helps patients understand the practical side of treatment, including insurance verification, out-of-network benefits, cost-share estimates, self-pay options, and billing questions. We believe patients should have as much clarity as possible before moving forward.

Insurance & Billing

Request a Hernia Pain Evaluation

If groin, abdominal, pelvic, hip-region, or upper thigh pain is persistent, unclear, or continuing after hernia repair, MPM can help evaluate what may be contributing. Our diagnosis-first approach considers true hernia pain, sports hernia, post-hernia repair nerve pain, ACNES, abdominal wall nerve entrapment, pelvic floor dysfunction, endometriosis, hypermobility, EDS, scar tissue, mesh-related irritation, and peripheral nerve entrapment. Request an appointment to discuss your symptoms and care options.

Request An Appointment

Insights & Research

Explore MPM Insights and Research, including patient-friendly articles, clinical perspectives, and research from our team to help explain how we understand complex pain, evaluate care options, and guide the path to treatment
Patient education

A Deeper Look at Hernia Pain, Groin Pain, and Abdominal Wall Nerve Pain

Hernia-related pain can involve structural, nerve-related, pelvic, abdominal wall, post-surgical, and musculoskeletal contributors.

Hernia Pain

Hernia pain can occur when tissue pushes through a weakened area in the abdominal wall, groin, or pelvic region. Some hernias cause a visible or palpable bulge. Others may cause pressure, aching, pulling, heaviness, sharp pain, or discomfort that worsens with coughing, lifting, standing, straining, exercise, or core activity.

Not all hernia-like pain is caused by a hernia. Groin, abdominal wall, pelvic, hip-region, and upper thigh pain can come from multiple sources. These may include a true hernia, sports hernia or athletic pubalgia, ACNES, abdominal wall nerve entrapment, peripheral nerve entrapment, pelvic floor dysfunction, endometriosis, hip pathology, anterior pelvic tilt, scar tissue, mesh-related irritation, or pain after hernia repair.

MPM evaluates hernia-related pain through a diagnosis-first lens. The goal is to determine whether a structural hernia needs surgical evaluation, whether pain is coming from a nerve or abdominal wall source, or whether several pain generators are interacting.

What Hernia Pain Can Feel Like

Hernia pain may feel like pressure, heaviness, aching, pulling, burning, sharp pain, or discomfort in the abdomen, groin, pelvis, hip-region, or upper thigh. Some patients notice a bulge that becomes more prominent with coughing, lifting, or standing. Others feel pain without a visible bulge.

Pain may worsen with straining, exercise, abdominal contraction, walking, bending, sex, bowel movements, or prolonged standing. In some patients, pain may be localized to one small tender area. In others, symptoms may spread into the groin, pelvis, thigh, lower abdomen, or hip region.

Because the symptom pattern can overlap with nerve, pelvic, hip, abdominal wall, and post-surgical pain, evaluation should confirm the likely source before treatment is selected.

Common Types of Hernia-Related Pain

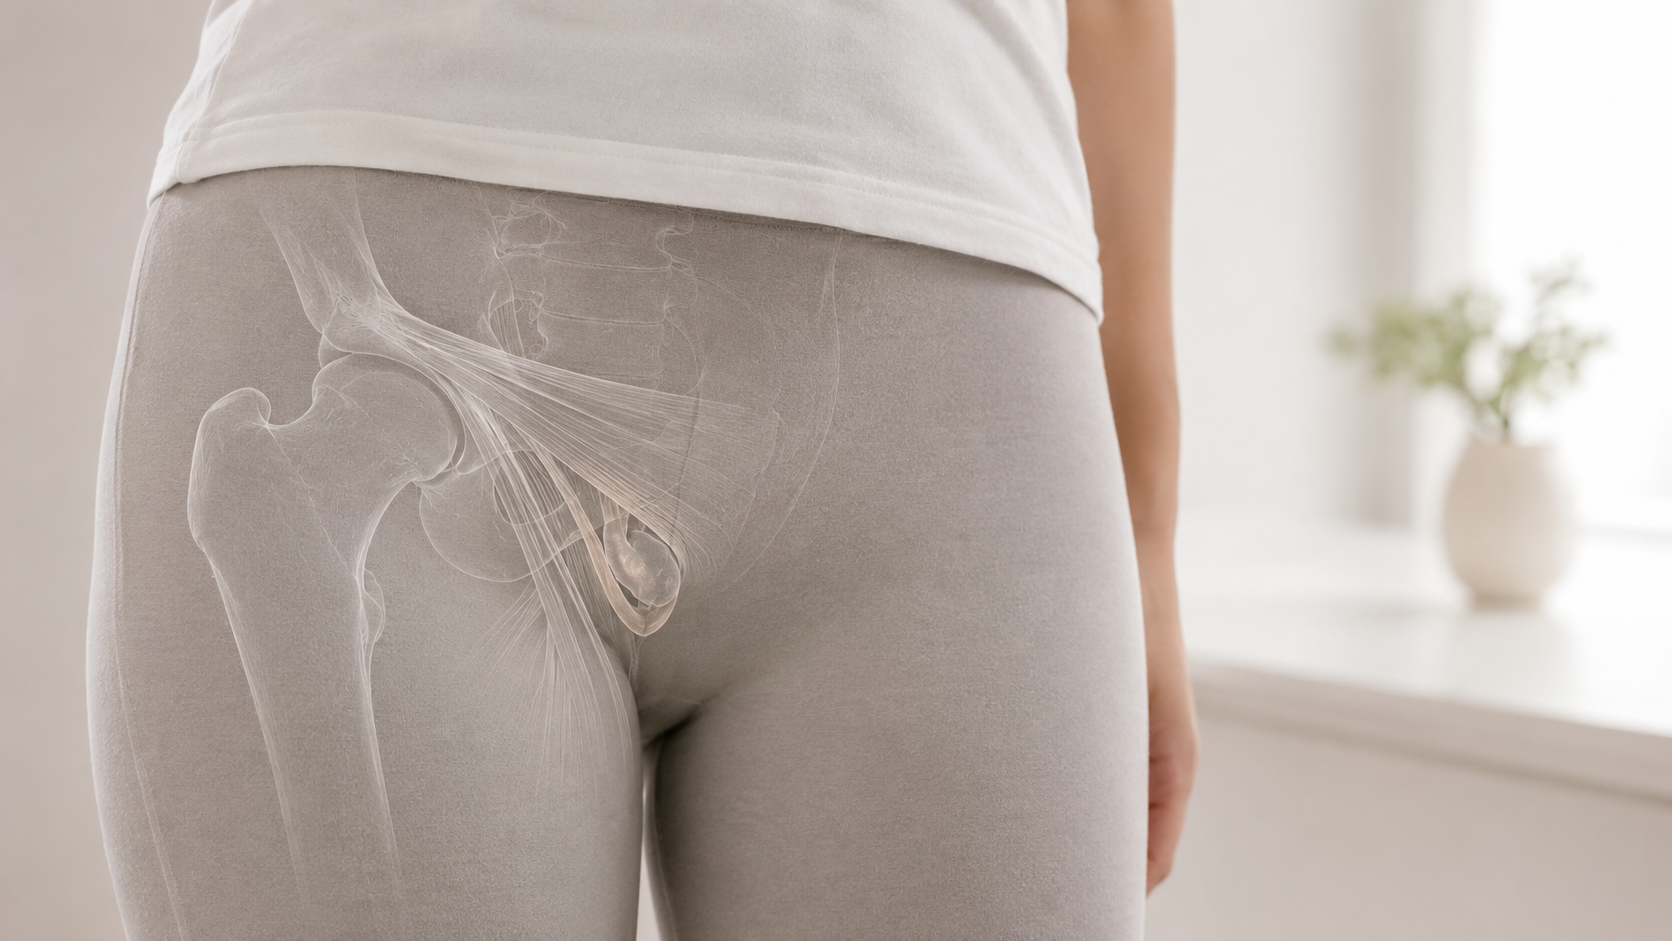
Hernia-related pain may come from several different regions. Inguinal hernia pain often appears in the groin and may worsen with lifting or straining. Femoral hernias may cause groin or upper thigh symptoms and may be more difficult to recognize. Obturator hernias are rare and can cause pelvic, medial thigh, abdominal, or bowel-related symptoms. Umbilical hernias may cause pain or pressure near the bellybutton.

Sports hernia or athletic pubalgia is different from a traditional hernia. It usually refers to a soft tissue injury involving the lower abdominal or groin region and may not create a visible bulge. It can cause pain with cutting, twisting, sprinting, sit-ups, kicking, or athletic movement.

Post-hernia repair pain may involve scar tissue, nerve irritation, mesh-related sensitivity, altered mechanics, or another pain source that was present before surgery.

Hernia Pain vs. Abdominal Wall Nerve Entrapment

Abdominal wall nerve entrapment can closely resemble hernia pain. ACNES is one example of abdominal wall nerve entrapment that can cause focal abdominal pain, tenderness, burning, sharp pain, or pain triggered by movement or pressure.

Unlike a structural hernia, nerve entrapment does not involve tissue pushing through a weakened area. The pain comes from irritation or compression of a nerve in the abdominal wall. Patients may have normal abdominal imaging or no visible bulge.

MPM evaluates whether symptoms suggest hernia, ACNES, peripheral nerve entrapment, post-surgical nerve irritation, pelvic floor dysfunction, or another pain generator. In selected cases, diagnostic ultrasound or targeted injections may help clarify the source.

Sports Hernia and Athletic Pubalgia

Sports hernia, also called athletic pubalgia, is a common source of confusion because it is not always a true hernia. It often involves injury or overload of the lower abdominal wall, adductor region, pubic area, or surrounding soft tissues.

Patients may feel groin pain, lower abdominal pain, pain with sprinting or cutting, pain with twisting, or pain during core activity. Symptoms may be mistaken for inguinal hernia, hip impingement, adductor strain, pelvic floor dysfunction, or nerve entrapment.

MPM evaluates sports hernia-type pain by reviewing movement triggers, athletic activity, pelvic mechanics, hip function, abdominal wall tenderness, nerve symptoms, and prior imaging. Surgical or sports medicine referral may be appropriate when structural repair or athletic pubalgia-specific care is needed.

Pain After Hernia Repair

Chronic pain after hernia repair can be frustrating, especially when the repair appears structurally successful but pain continues. Pain may involve nerve irritation, scar tissue, mesh-related sensitivity, local inflammation, altered abdominal wall mechanics, or another condition that overlaps with the original hernia pain.

Symptoms may feel burning, sharp, pulling, tight, electric, or pressure-like. Pain may occur near the incision, mesh region, groin, lower abdomen, pelvis, or upper thigh. Some patients feel pain with movement, touch, sitting, standing, lifting, sex, or exercise.

MPM reviews the surgical history, pain location, timing, nerve distribution, scar sensitivity, imaging, and prior treatment response. If surgical complications or recurrent hernia are suspected, MPM coordinates with the appropriate surgeon.

Hernia Pain, Pelvic Pain, and Pelvic Floor Dysfunction

Groin and pelvic-region pain can overlap with pelvic floor dysfunction. Tight, overactive, weak, or poorly coordinated pelvic floor muscles may contribute to pain with sitting, sex, bowel movements, urination, exercise, or core activity. Pelvic floor dysfunction can also coexist with hernia, sports hernia, endometriosis, pudendal neuralgia, hip pathology, or abdominal wall nerve pain.

Because these systems are connected, pain may not stay in one location. A patient may feel lower abdominal pain, groin pain, pelvic pressure, hip pain, thigh pain, or nerve-like symptoms.

MPM evaluates pelvic-region pain in context and coordinates with pelvic floor physical therapy, gynecology, urology, gastroenterology, general surgery, orthopedics, or other specialists when appropriate.

Hernia Pain, Hypermobility, and EDS

Hypermobility spectrum disorder and Ehlers-Danlos syndrome may complicate abdominal, groin, and pelvic-region pain. Connective tissue laxity may affect joint stability, pelvic mechanics, abdominal wall support, and recovery from injuries or surgery. Some patients with hypermobility also experience recurrent sprains, pelvic instability, nerve irritation, or chronic pain sensitization.

This does not mean that every hernia or groin pain pattern is caused by hypermobility. It means that the evaluation should consider tissue behavior, mechanical stress, joint stability, and overlapping pain patterns when symptoms are persistent or complex.

MPM considers hypermobility and EDS when the history suggests multi-joint symptoms, recurrent injuries, pelvic instability, scar sensitivity, or chronic pain patterns that do not fit one simple diagnosis.

How MPM Evaluates Hernia-Related Pain

MPM begins with a detailed history and physical exam. The evaluation reviews pain location, quality, triggers, bulging, bowel or urinary symptoms, prior imaging, prior hernia repair, mesh or scar concerns, pelvic symptoms, abdominal wall tenderness, nerve distribution, hip mechanics, activity pattern, and prior treatment response.

Diagnostic ultrasound may be considered when the clinical question involves abdominal wall structures, groin soft tissue, nerve-related pain, scar tissue, or dynamic pain patterns. Ultrasound may also help guide selected procedures when a specific target is identified.

When symptoms suggest a surgically significant hernia, MPM coordinates with general surgery or the appropriate specialist. When symptoms suggest nerve-related or post-surgical pain, the care plan may focus on the identified pain generator rather than the hernia label alone.

Treatment Options for Hernia-Related Pain

Treatment depends on the cause of pain. A hernia that requires repair should be evaluated by a surgeon. Pain medicine does not replace surgical care for incarcerated, strangulated, obstructed, enlarging, or otherwise clinically significant hernias.

When pain is chronic, post-surgical, abdominal wall-related, pelvic-region, or nerve-related, treatment may include medication management when appropriate, diagnostic ultrasound, ultrasound-guided injections, steroid injections in selected cases, nerve hydrodissection for selected entrapment patterns, peripheral nerve stimulation for selected chronic nerve pain, acupuncture, and coordinated pelvic or musculoskeletal care.

The goal is to treat the pain generator, not simply the painful area. For example, post-hernia repair nerve pain may require a different plan than pelvic floor dysfunction, ACNES, athletic pubalgia, or true recurrent hernia.

When Nerve Hydrodissection or Peripheral Nerve Stimulation May Be Considered

Nerve hydrodissection may be considered in selected nerve entrapment patterns when imaging, anatomy, symptoms, and exam findings support that approach. It is not a standard treatment for all hernia pain and should not be used as a substitute for surgical evaluation when a hernia requires repair.

Peripheral nerve stimulation may be considered for selected chronic nerve pain patterns when conservative and less invasive options have not provided sufficient relief and when the nerve target and clinical pattern are appropriate. It is not used for every patient and requires careful evaluation, risk discussion, and follow-up.

When Hernia Pain Requires Urgent Evaluation

Patients should seek urgent evaluation for severe or worsening abdominal or groin pain, a bulge that cannot be pushed back in, nausea, vomiting, abdominal distension, inability to pass stool or gas, fever, skin discoloration over the bulge, fainting, severe testicular pain, severe pelvic pain, signs of bowel obstruction, or rapidly worsening symptoms.

These symptoms may suggest incarceration, strangulation, bowel obstruction, infection, vascular compromise, or another urgent medical condition. Pain medicine care should not delay emergency or surgical evaluation when red flags are present.

How MPM Approaches Hernia Pain Care

MPM approaches hernia pain through a diagnosis-first, coordinated model. The goal is to determine whether pain is structural, surgical, nerve-related, abdominal wall-related, pelvic, musculoskeletal, post-surgical, or mixed.

For patients looking for hernia pain treatment in Manhattan or NYC, MPM offers a careful pain medicine perspective focused on pain generator identification, diagnostic ultrasound when appropriate, nerve-focused evaluation, pelvic pain overlap, and coordination with the right specialists. Treatment is individualized and selected only after the likely source of pain is better understood.