Spondylosis
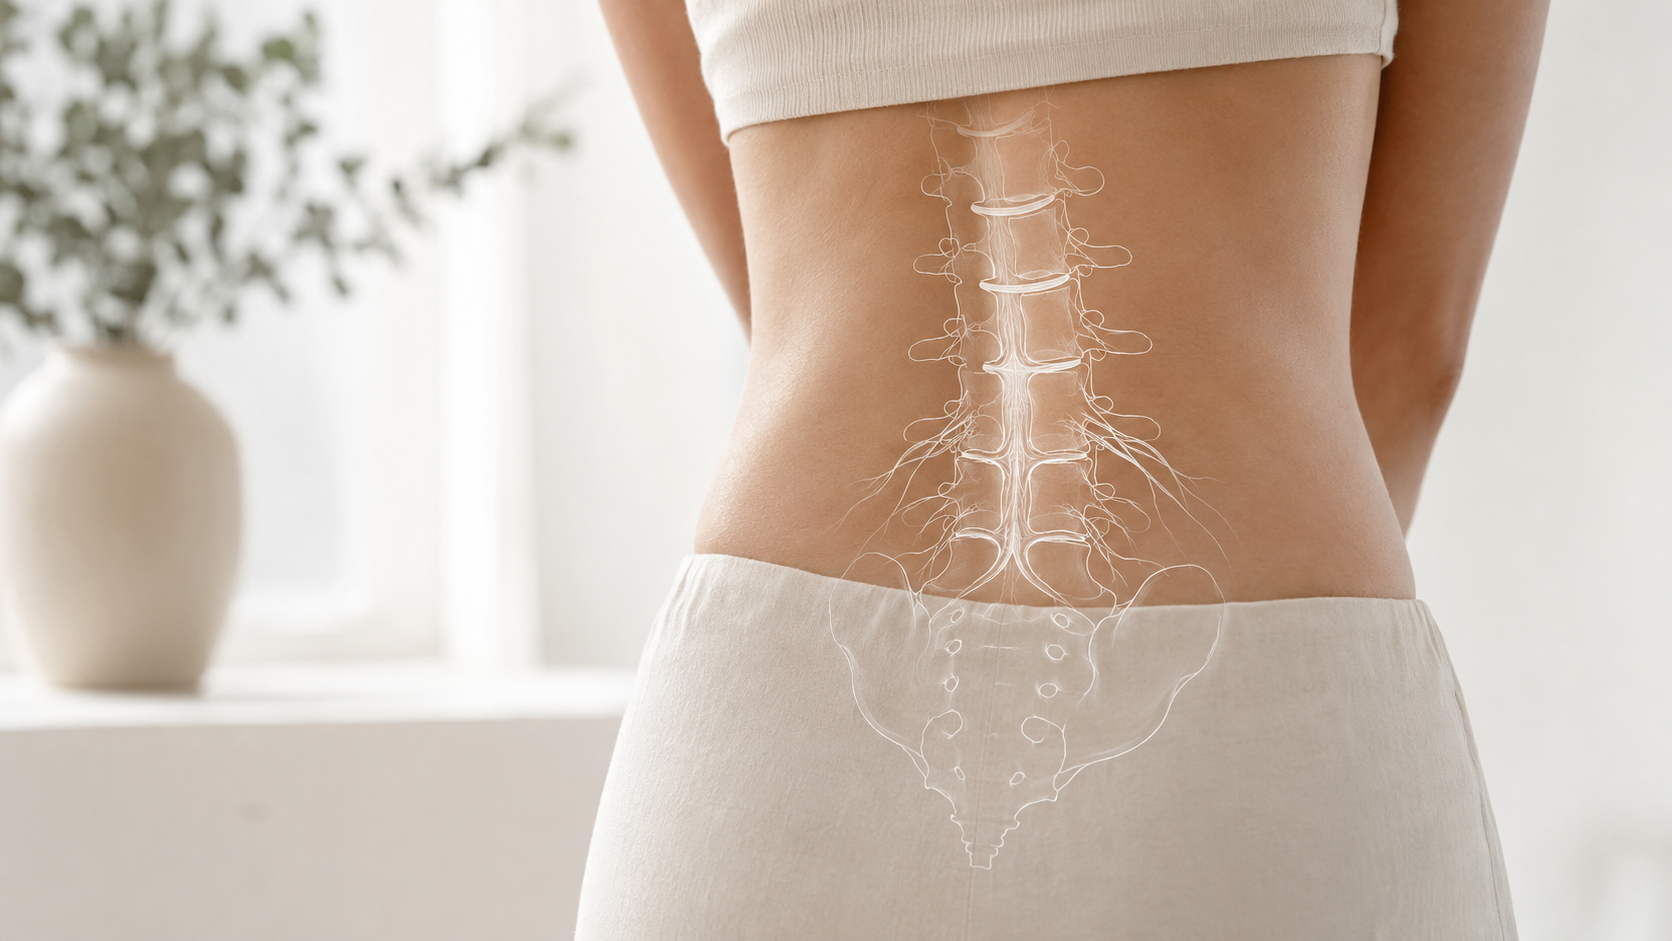
Spondylosis is a broad term used to describe degenerative changes in the spine. These changes may involve the discs, facet joints, ligaments, vertebrae, bone spurs, and surrounding muscles. It can occur in the neck, mid-back, or lower back.
Many patients first hear the word spondylosis after an MRI, CT scan, or X-ray. The term can sound alarming, but it does not automatically mean something dangerous is happening. Degenerative spine changes are common, especially with age. The important question is whether those changes match the patient’s symptoms.
At MPM, the evaluation focuses on identifying the true pain generator. Spondylosis may contribute to pain, but it may also coexist with herniated discs, spinal stenosis, spondylolisthesis, facet arthropathy, SI joint dysfunction, inflammatory spine disease, hypermobility, nerve irritation, muscle guarding, or chronic pain sensitization.
Cervical, Thoracic, and Lumbar Spondylosis
Cervical spondylosis affects the neck. It may cause neck pain, stiffness, limited range of motion, headaches, shoulder discomfort, or arm symptoms if nerves are irritated. Some patients notice pain when turning the head, looking up, working at a computer, driving, or holding the neck in one position for long periods.
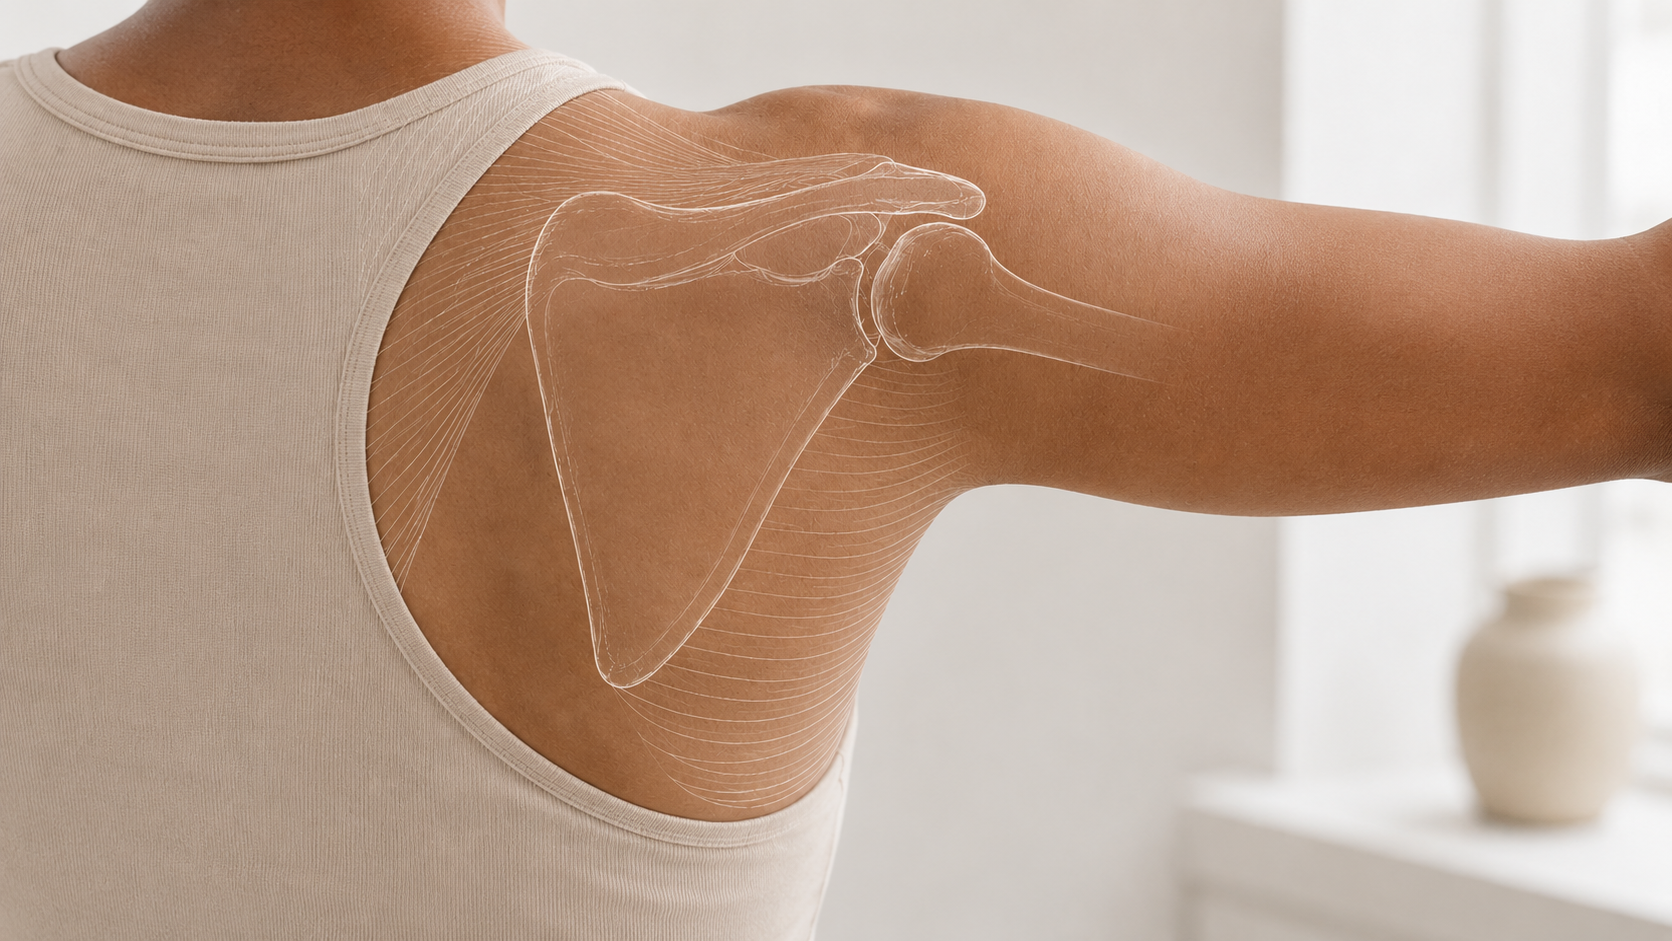
Thoracic spondylosis affects the mid-back. It may contribute to stiffness, rib-region pain, pain between the shoulder blades, or discomfort with posture and rotation. Thoracic pain can overlap with slipping rib syndrome, scapular dyskinesia, thoracic outlet-type symptoms, inflammatory spine pain, and muscle pain.
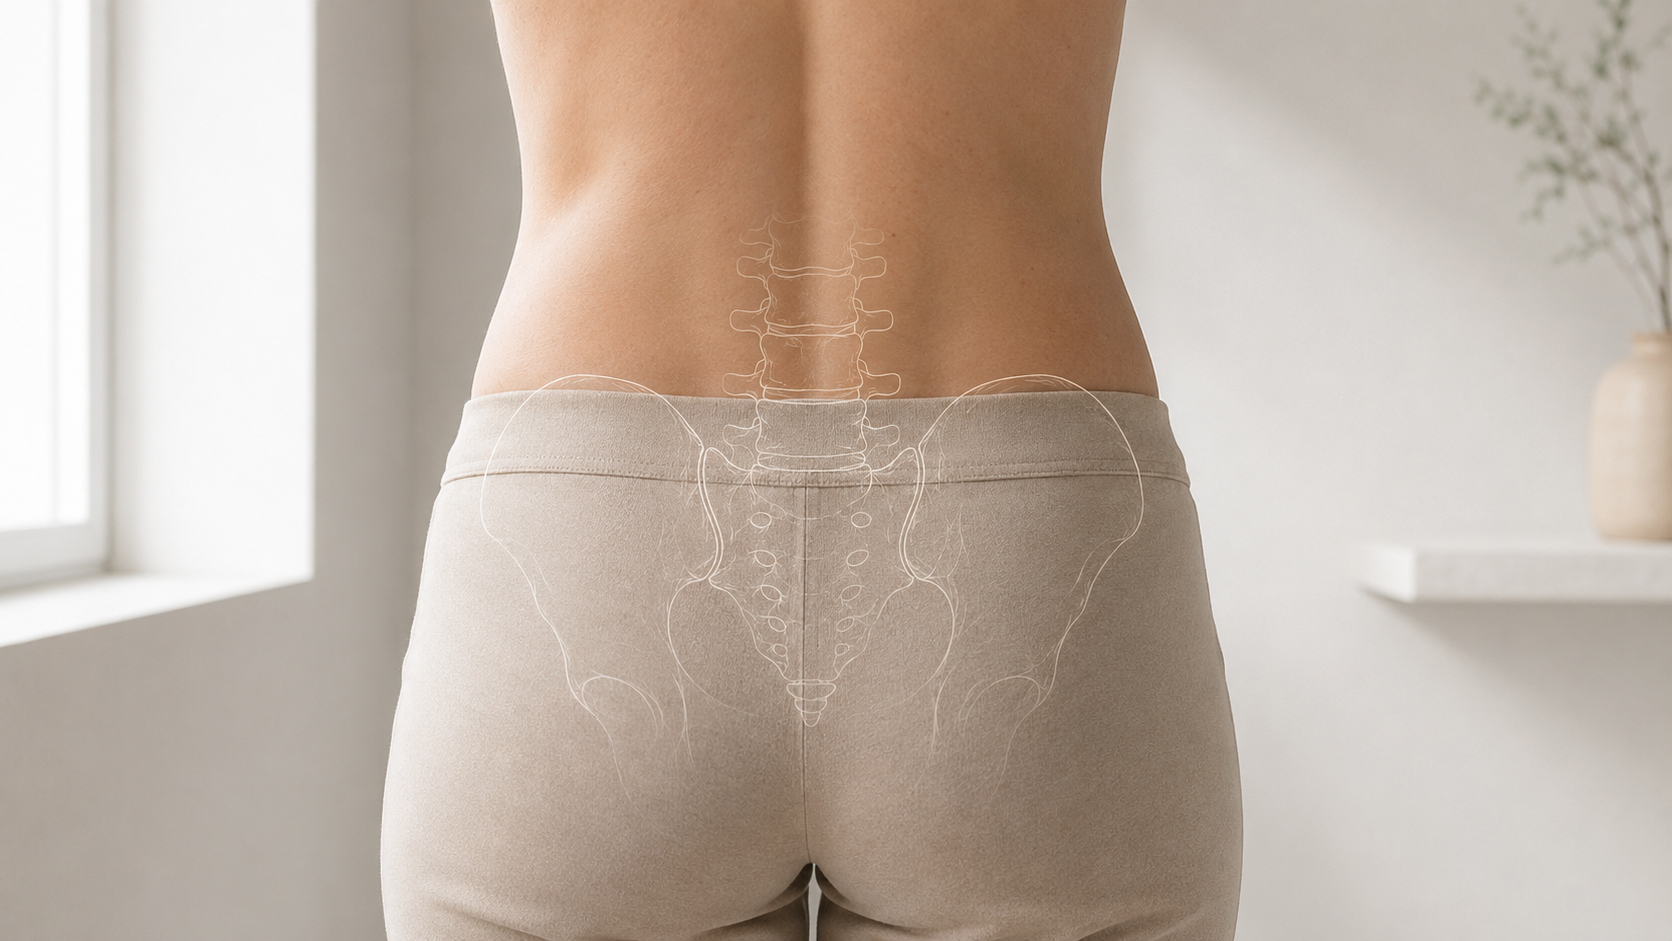
Lumbar spondylosis affects the lower back. It may cause low back pain, stiffness, pain with standing or walking, buttock pain, hip-region pain, or leg symptoms when nerves are involved. Lumbar spondylosis can overlap with spinal stenosis, sciatica, herniated discs, spondylolisthesis, SI joint dysfunction, and hip or pelvic conditions.
Spondylosis, Spine Arthritis, and Degenerative Disc Changes
Spondylosis often includes arthritis-like changes in the facet joints. Facet joints are small joints in the back of the spine that help guide movement. When these joints become irritated or arthritic, patients may feel pain with extension, twisting, standing, or certain positions.
Spondylosis may also include disc degeneration. Discs can lose hydration or height over time, which may change how force moves through the spine. In some cases, disc changes may irritate nearby nerves or contribute to stenosis. In other cases, disc degeneration is visible on imaging but not the main source of pain.
Bone spurs may also form as part of degenerative change. Bone spurs do not always cause symptoms, but they can contribute to nerve compression if they narrow the space around spinal nerves.
Spondylosis vs Herniated Disc
Spondylosis describes broader degenerative spine changes. A herniated disc is a more specific condition in which disc material pushes outward and may irritate a nearby nerve. A patient can have both conditions at the same time.
The distinction matters because treatment depends on the pain generator. A herniated disc may cause acute radiating nerve pain, while spondylosis may contribute to chronic stiffness, facet pain, stenosis, or mechanical spine pain. MPM reviews imaging, symptoms, and exam findings together to determine which finding is clinically important.
Spondylosis vs Spinal Stenosis
Spinal stenosis refers to narrowing of the spinal canal or nerve openings. Spondylosis can contribute to stenosis through disc changes, bone spurs, facet enlargement, or ligament thickening.
When stenosis affects nerves, patients may experience pain, heaviness, numbness, tingling, or weakness in the legs or arms. Lumbar stenosis may worsen with standing or walking and improve with sitting or leaning forward. Cervical stenosis can be more concerning if it affects the spinal cord, especially when symptoms include hand clumsiness, balance changes, weakness, or coordination problems.
Spondylosis vs Spondylolisthesis
Spondylolisthesis occurs when one vertebra slips out of alignment with the vertebra below it. Spondylosis refers to degenerative changes. These conditions may overlap because degeneration can contribute to instability, and instability can increase stress on discs and joints.
MPM evaluates whether symptoms are coming from the vertebral slip, degenerative joints, stenosis, disc disease, SI joint dysfunction, hypermobility, or another pain source.
Why Degenerative Changes Do Not Always Equal Pain
Many people have degenerative spine findings on imaging without significant symptoms. This is why pain should not be explained by the MRI alone. A patient’s scan may show spondylosis, but the true pain generator may be the SI joint, a nerve root, a muscle pattern, inflammatory disease, hip pathology, or chronic pain sensitization.
MPM uses a diagnosis-first process to avoid treating the wrong structure. The evaluation includes pain pattern analysis, movement testing, neurologic screening, imaging review, prior treatment history, and assessment for overlapping musculoskeletal or inflammatory contributors.
Spondylosis and Nerve Symptoms
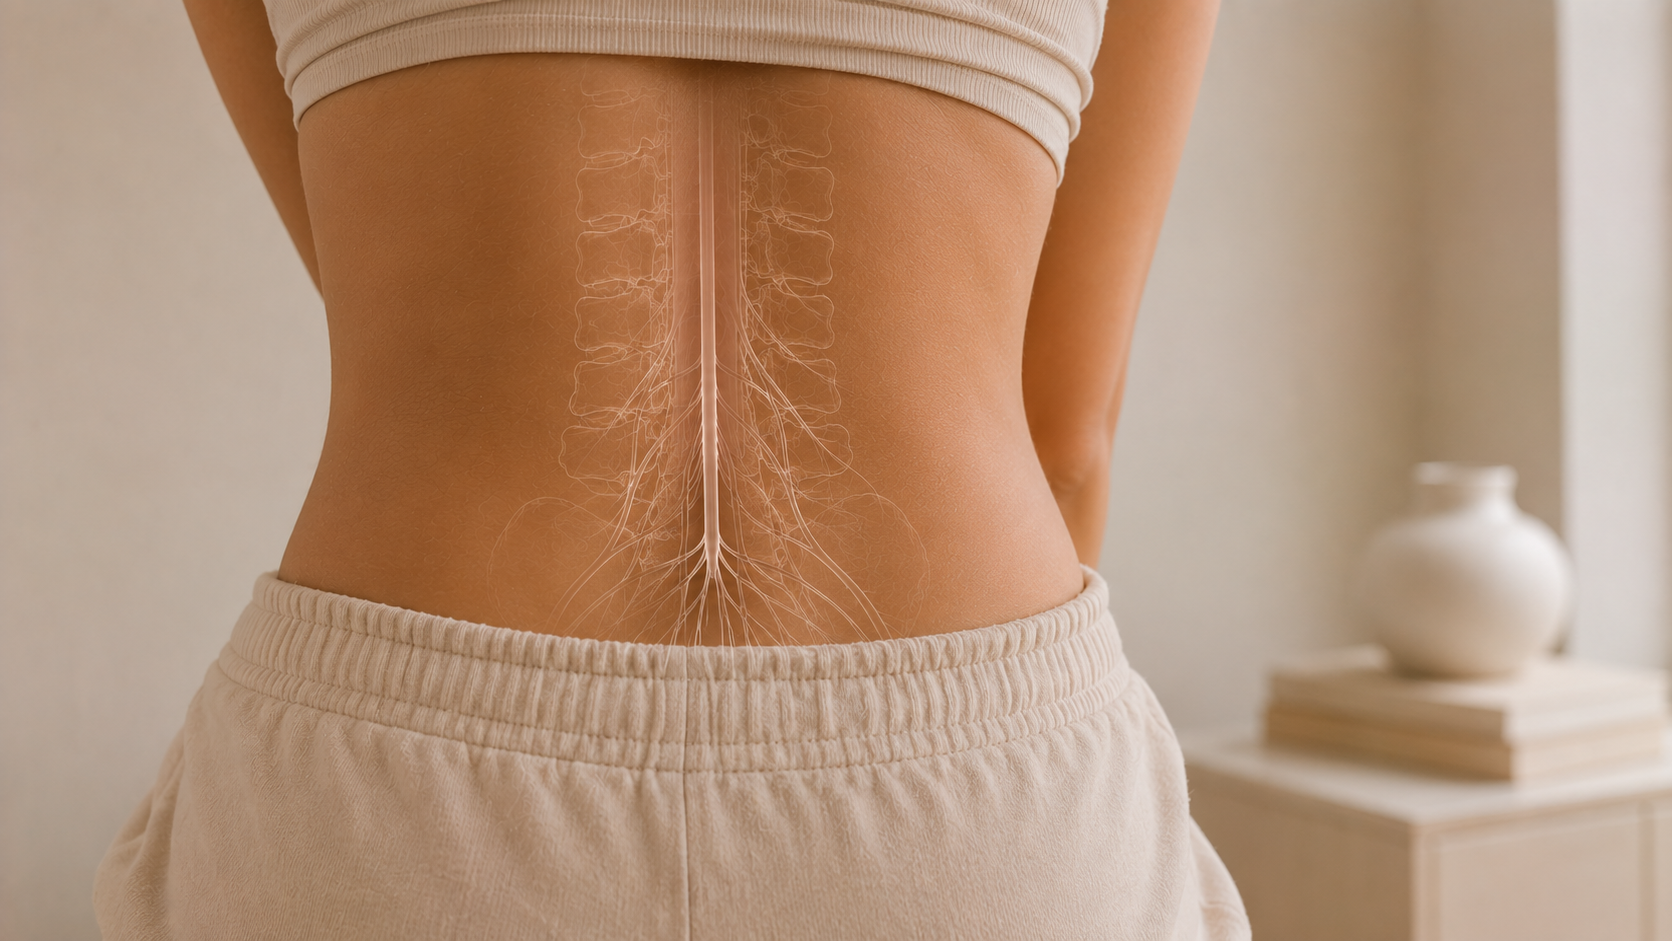
Spondylosis may cause nerve symptoms when degenerative changes narrow the space around a nerve root or spinal cord. Patients may describe burning, tingling, numbness, weakness, heaviness, or pain traveling into the arm or leg.
In the neck, nerve irritation may cause symptoms into the shoulder, arm, hand, or fingers. In the lower back, nerve irritation may cause symptoms into the buttock, thigh, leg, or foot. These patterns may resemble cervical radiculopathy, lumbar radiculopathy, sciatica, peripheral neuropathy, or nerve entrapment.
Because nerve symptoms can come from many sources, MPM evaluates the full pathway before recommending treatment.
Spondylosis, Hypermobility, and Complex Spine Pain
In patients with hypermobility spectrum disorder or Ehlers-Danlos syndrome, spine pain can be more complex. Joint laxity, muscle guarding, altered proprioception, recurrent injuries, and instability may change how the spine absorbs load.
Spondylosis can still occur in hypermobile patients, but the symptoms may not behave like typical degenerative spine pain. Some patients experience recurrent flares, shifting pain, muscle tightness, headaches, SI joint pain, or nerve sensitivity. MPM evaluates hypermobility as one part of the clinical picture, not as an automatic explanation for every symptom.
Inflammatory Spine Pain and Spondylosis
Degenerative spine pain and inflammatory spine pain can overlap. Conditions such as seronegative spondyloarthropathy, autoimmune-related pain, rheumatoid arthritis, Sjogren’s, or enthesitis may contribute to stiffness, joint pain, tendon pain, or spine symptoms.
Inflammatory back pain may be more noticeable in the morning, improve with movement, worsen with rest, or occur with other inflammatory symptoms. MPM considers these patterns and may coordinate with rheumatology when autoimmune or inflammatory disease may be contributing.
How MPM Evaluates Spondylosis
MPM begins with a detailed history and physical exam. The evaluation reviews where pain occurs, how long it has been present, what movements worsen it, whether symptoms travel into the arms or legs, whether there is numbness or weakness, and how symptoms affect work, sleep, exercise, walking, or daily function.
The exam may include spine movement testing, neurologic screening, strength and sensation testing, gait assessment, SI joint and hip screening, and evaluation for muscle guarding or hypermobility when relevant. Imaging is reviewed in context rather than treated as the diagnosis by itself.
When symptoms suggest progressive neurologic involvement, inflammatory disease, vascular concerns, infection, fracture, or surgical pathology, MPM coordinates referral to the appropriate specialist.
Treatment Options for Spondylosis
Treatment depends on the main pain generator and the patient’s goals. Many patients begin with conservative care, especially when there are no urgent neurologic findings.
Conservative care may include physical therapy coordination, movement retraining, activity modification, posture and ergonomic changes, weight management when relevant, acupuncture, Feldenkrais, biofeedback, pain psychology, and medication management when appropriate.
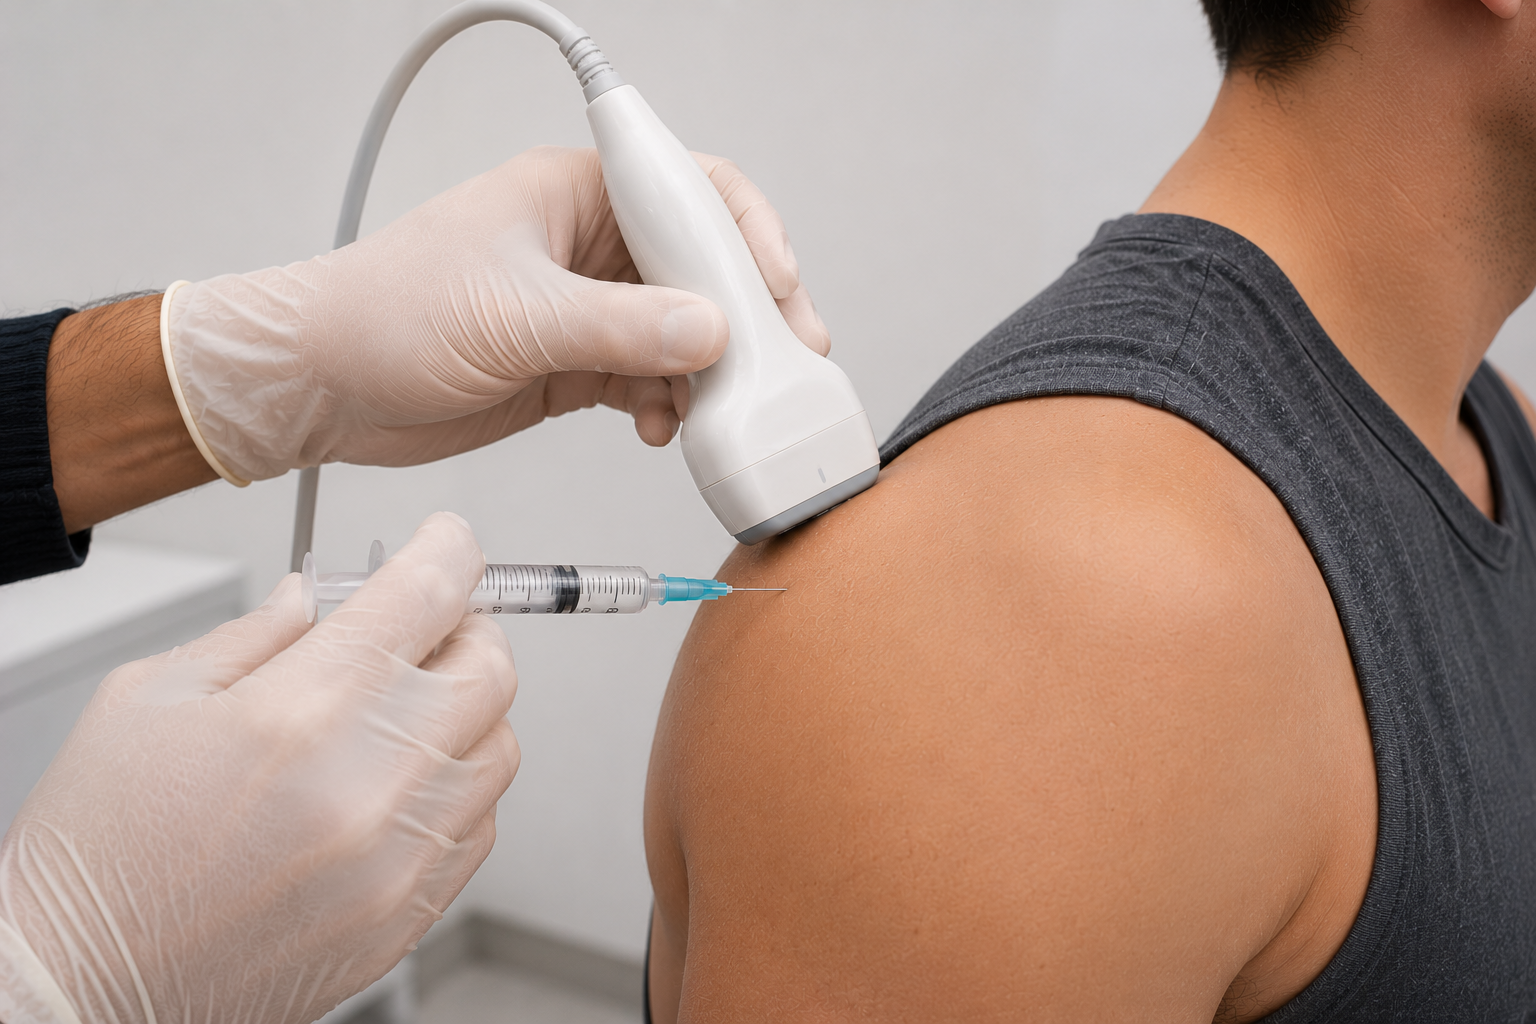
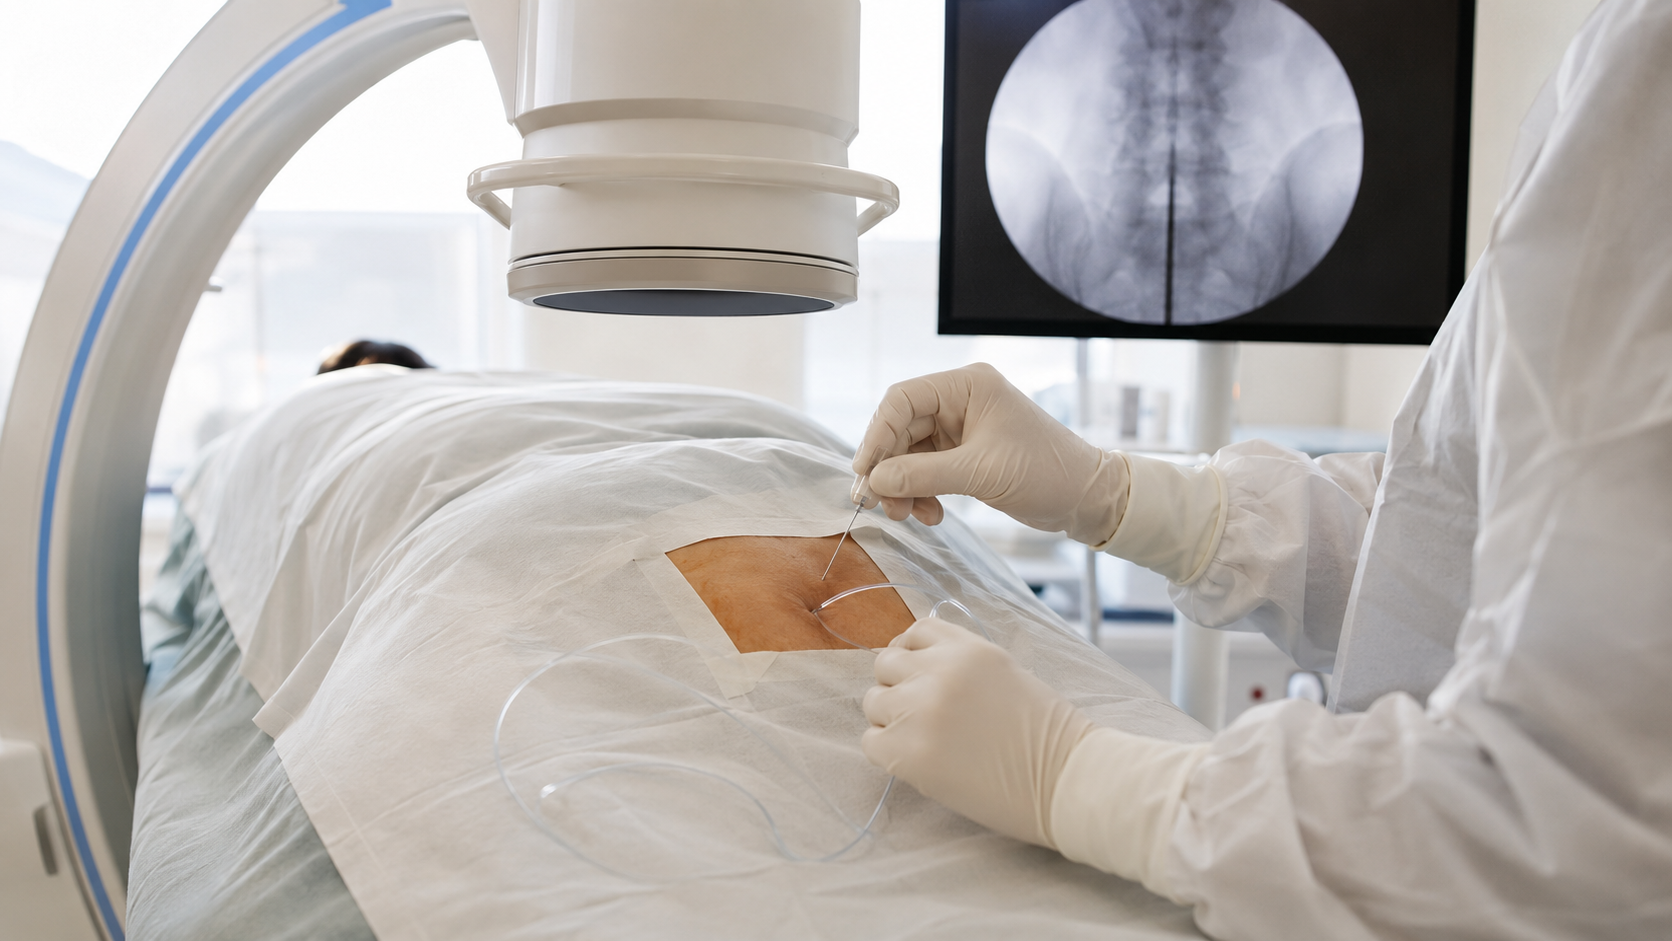
When a specific pain generator is identified, image-guided procedures may be considered. These may include epidural injections for nerve irritation, steroid injections in selected cases, or other spine-related procedures depending on the diagnosis. For persistent neuropathic or complex spine pain, advanced options such as spinal cord stimulation or dorsal root ganglion stimulation may be discussed in carefully selected patients.
These treatments are not routine for every case of spondylosis. They require diagnosis-specific evaluation, risk discussion, and clinician supervision.
Image-Guided Spine Procedures and Advanced Pain Options
Image-guided spine procedures may help when symptoms are linked to a specific structure, such as a nerve root, facet joint, SI joint, or area of inflammation. In some cases, these procedures may have both diagnostic and therapeutic value. A response to an injection can help clarify whether the targeted structure is contributing to pain.
Advanced pain options may be considered when pain is persistent, nerve-related, and functionally limiting despite appropriate conservative and interventional care. These options require careful selection and are not appropriate for every patient.
When Surgical Evaluation May Be Needed
Spondylosis is not automatically a surgical condition. Many patients can manage symptoms without surgery. However, surgical evaluation may be appropriate when there is progressive weakness, spinal cord compression, severe stenosis, disabling nerve symptoms, structural instability, or pain that remains severe despite appropriate nonsurgical care.
MPM helps patients understand when pain medicine care is appropriate and when spine surgery or neurosurgery input is needed.
Coordinated Care for Degenerative and Complex Spine Pain
Spondylosis often occurs alongside other pain generators. A patient may have facet arthropathy, disc degeneration, spinal stenosis, SI joint dysfunction, inflammatory pain, hypermobility, muscle guarding, peripheral neuropathy, or chronic pain sensitization at the same time. Treating only one imaging finding may not address the full problem.
MPM’s role is to identify the most relevant pain generators, create a stepwise care plan, coordinate with other specialists when needed, and help patients move toward better function with careful treatment selection.
When Symptoms Require Urgent Evaluation
Patients should seek urgent evaluation for new or worsening weakness, trouble walking, loss of coordination, bowel or bladder dysfunction, saddle anesthesia, progressive numbness, fever, unexplained weight loss, history of cancer, major trauma, severe night pain, chest pain, shortness of breath, or rapidly worsening symptoms.
Spondylosis-like symptoms can overlap with herniated disc, spinal stenosis, spondylolisthesis, facet arthropathy, SI joint dysfunction, hip disease, inflammatory spine disease, peripheral neuropathy, vascular disease, infection, fracture, malignancy, and central pain syndromes. Red flags should not be ignored.
How MPM Approaches Spondylosis Care
MPM approaches spondylosis through a diagnosis-first model. The goal is not simply to treat degeneration. The goal is to understand whether degenerative spine changes are causing pain, whether another structure is more important, or whether multiple pain generators are interacting.
For patients looking for spondylosis treatment in Manhattan or NYC, MPM provides careful evaluation of neck pain, back pain, stiffness, nerve symptoms, spinal stenosis overlap, hypermobility-related complexity, inflammatory pain patterns, and chronic spine pain. Treatment is individualized and may include conservative care, medication management, image-guided procedures, advanced pain options for selected patients, and referral for surgical evaluation when appropriate.